
Scoliosis
Scoliosis causes a sideways curve of your backbone, or spine. These curves are often S- or C-shaped. Scoliosis is most common in late childhood and the early teens, when children grow fast. Girls are more likely to have it than boys. It can run in families. Symptoms include leaning to one side and having uneven shoulders and hips. Sometimes it is easy to notice, but not always.
Children may get screening for scoliosis at school or during a checkup. If it looks like there is a problem, your doctor will use your medical and family history, a physical exam, and imaging tests to make a diagnosis. Treatment depends on your age, how much more you're likely to grow, how much curving there is, and whether the curve is temporary or permanent. People with mild scoliosis might only need checkups to see if the curve is getting worse. Others might need to wear a brace or have surgery.
NIH: National Institute of Arthritis and Musculoskeletal and Skin Diseases
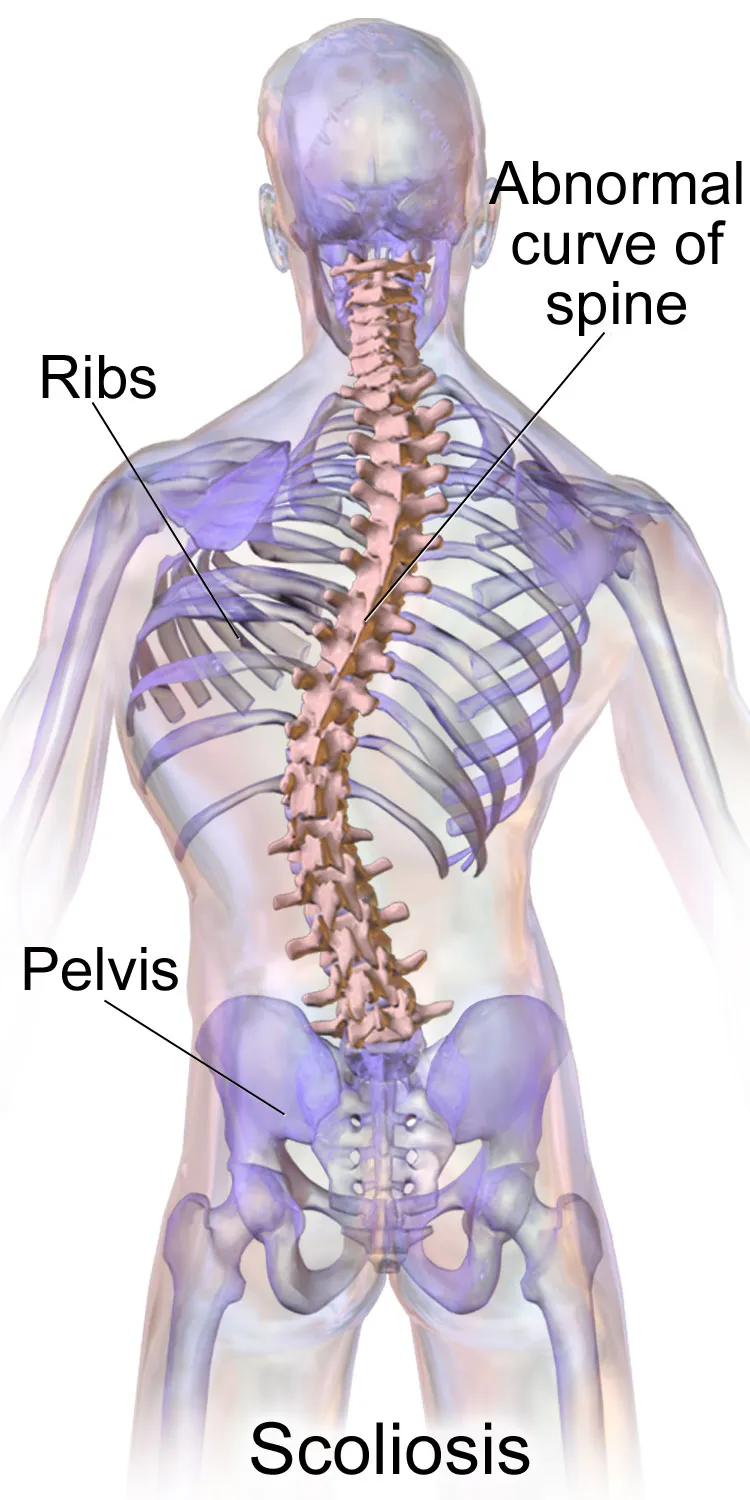
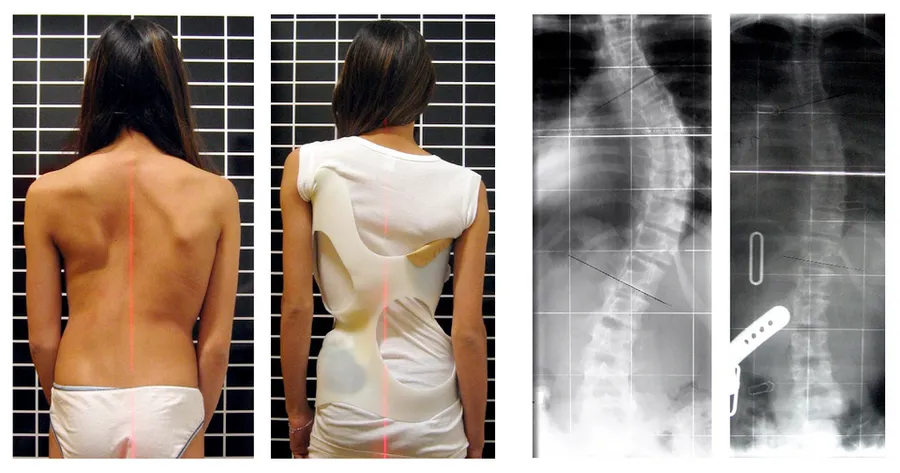
Signs and symptoms
Symptoms associated with scoliosis can include:
Pain in the back at the site of the curve, which may radiate to the legs. Chest pain at the ribs and sternum location can sometimes be linked to scoliosis of the spine because the ribs wrap around to the chest area which can be misaligned. This can lead to injury, pain and swelling which can turn up on medical imaging (CT scans etc.).
Respiratory or cardiac problems in severe cases
Constipation due to curvature causing "tightening" of the stomach, intestines, etc.
Pain, weakness, or numbness in the lower limbs, difficulty bending forward, and uneven alignment of the pelvis and hips may also be present.
Uneven musculature on one side of the spine
Rib prominence or a prominent shoulder blade, caused by rotation of the rib cage in thoracic scoliosis
Calcium deposits in the cartilage endplate and sometimes in the disc itself
Course
People who have reached skeletal maturity are less likely to have a worsening case. Some severe cases of scoliosis can lead to diminishing lung capacity, pressure exerted on the heart, and restricted physical activities.
Longitudinal studies have revealed that the most common form of the condition, late-onset idiopathic scoliosis, causes little physical impairment other than back pain and cosmetic concerns, even when untreated, with mortality rates similar to the general population. Older beliefs that untreated idiopathic scoliosis necessarily progressed into severe (cardiopulmonary) disability by old age have been refuted.
Causes
An estimated 65% of scoliosis cases are idiopathic (cause unknown), about 15% are congenital, and about 10% are secondary to a neuromuscular disease.
About 38% of variance in scoliosis risk is due to genetic factors, and 62% is due to the environment. The genetics are likely complex, given the inconsistent inheritance and discordance among monozygotic twins. The specific genes that contribute to the development of scoliosis have not been conclusively identified. Several candidate gene studies have found associations between idiopathic scoliosis and genes mediating bone formation, bone metabolism, and connective tissue structure. Several genome-wide studies have identified several loci as significantly linked to idiopathic scoliosis. In 2006, idiopathic scoliosis was linked with three microsatellite polymorphisms in the MATN1 gene (encoding for matrilin 1, cartilage matrix protein). Fifty-three single nucleotide polymorphism markers in the DNA that are significantly associated with adolescent idiopathic scoliosis were identified through a genome-wide association study. Abnormalities in bone metabolism have also been investigated as potential contributing factors, with studies reporting lower bone mass in adolescents with idiopathic scoliosis compared to controls.
Adolescent idiopathic scoliosis has no clear causal agent and is generally believed to be multifactorial, leading to "progressive functional limitations" for individuals. Research suggests that Posterior Spinal Fusion (PSF) can be used to correct the more severe deformities caused by adolescent idiopathic scoliosis. Such procedures can result in a return to physical activity in about 6 months, which is very promising, although minimal back pain is still to be expected in the most severe cases. The prevalence of scoliosis is 1–2% among adolescents, but the likelihood of progression among adolescents with a Cobb angle less than 20° is about 10–20%.
Congenital scoliosis can be attributed to a malformation of the spine during weeks three to six in utero due to a failure of formation, a failure of segmentation, or a combination of stimuli. Incomplete and abnormal segmentation results in an abnormally shaped vertebra, at times fused to a normal vertebra or unilaterally fused vertebrae, leading to the abnormal lateral curvature of the spine.
Vertebrae of the spine, especially in the thoracic region, are, on average, asymmetric. The mid-axis of these vertebral bodies tends to point systematically to the right of the median body plane. A strong asymmetry of the vertebrae and their musculature, may lead to mechanical instability of the column, especially during phases of rapid growth. The asymmetry is thought to be caused by an embryological twist of the body.
Resulting from other conditions
Secondary scoliosis due to neuropathic and myopathic conditions can lead to a loss of muscular support for the spinal column so that the spinal column is pulled in abnormal directions. Some conditions which may cause secondary scoliosis include muscular dystrophy, spinal muscular atrophy, poliomyelitis, cerebral palsy, spinal cord trauma, and myotonia. Scoliosis often presents itself, or worsens, during an adolescent's growth spurt and is more often diagnosed in females than males.
Scoliosis associated with known syndromes is often subclassified as "syndromic scoliosis". Scoliosis can be associated with amniotic band syndrome, Arnold–Chiari malformation, Charcot–Marie–Tooth disease, cerebral palsy, congenital diaphragmatic hernia, connective tissue disorders, muscular dystrophy, familial dysautonomia, CHARGE syndrome, Ehlers–Danlos syndrome (hyperflexibility, "floppy baby" syndrome, and other variants of the condition), fragile X syndrome, Friedreich's ataxia, hemihypertrophy, Loeys–Dietz syndrome, Marfan syndrome, nail–patella syndrome, neurofibromatosis, osteogenesis imperfecta, Prader–Willi syndrome, proteus syndrome, spina bifida, spinal muscular atrophy, syringomyelia, and pectus carinatum.
Another form of secondary scoliosis is degenerative scoliosis, also known as de novo scoliosis, which develops later in life secondary to degenerative (may or may not be associated with aging) changes. This is a type of deformity that starts and progresses because of the collapse of the vertebral column in an asymmetrical manner. As bones start to become weaker and the ligaments and discs located in the spine become worn as a result of age-related changes, the spine begins to curve.
Diagnosis
People who initially present with scoliosis undergo a physical examination to determine whether the deformity has an underlying cause and to exclude the possibility of the more serious underlying condition than simple scoliosis.
The person's gait is assessed, with an exam for signs of other abnormalities (e.g., spina bifida as evidenced by a dimple, hairy patch, lipoma, or hemangioma). A thorough neurological examination is also performed, the skin for café au lait spots, indicative of neurofibromatosis, the feet for cavovarus deformity, abdominal reflexes and muscle tone for spasticity.
When a person can cooperate, they are asked to bend forward as far as possible. This is known as the Adams forward bend test and is often performed on school students. If a prominence is noted, then scoliosis is a possibility, and an X-ray may be done to confirm the diagnosis.
As an alternative, a scoliometer may be used to diagnose the condition.
When scoliosis is suspected, weight-bearing, full-spine AP/coronal (front-back view) and lateral/sagittal (side view) X-rays are usually taken to assess the scoliosis curves and the kyphosis and lordosis, as these can also be affected in individuals with scoliosis. Full-length standing spine X-rays are the standard method for evaluating the severity and progression of scoliosis, and whether it is congenital or idiopathic in nature. In growing individuals, serial radiographs are obtained at 3- to 12-month intervals to follow curve progression, and, in some instances, MRI investigation is warranted to look at the spinal cord. An average scoliosis patient has been in contact with around 50–300 mGy of radiation due to these radiographs during this period.
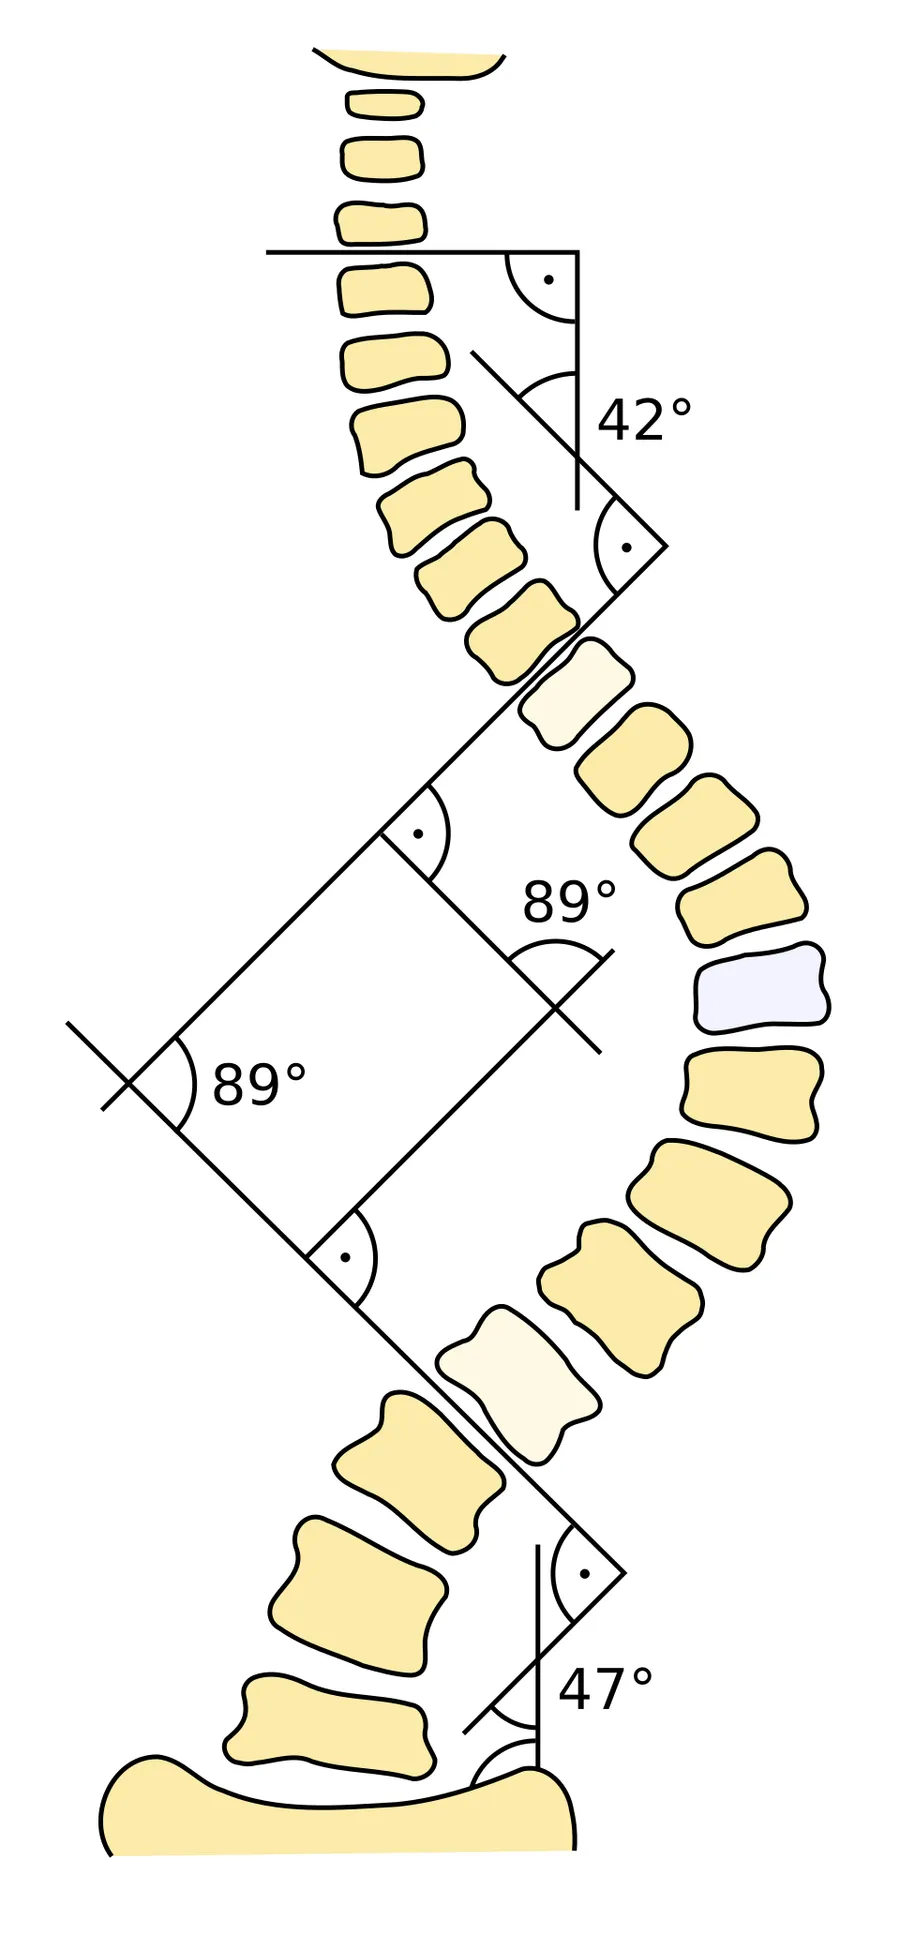
The standard method for assessing the curvature quantitatively is measuring the Cobb angle, which is the angle between two lines, drawn perpendicular to the upper endplate of the uppermost vertebra involved and the lower endplate of the lowest vertebra involved. For people with two curves, Cobb angles are followed for both curves. In some people, lateral-bending X-rays are obtained to assess the flexibility of the curves or the primary and compensatory curves.
Congenital and idiopathic scoliosis that develops before the age of 10 is referred to as early-onset scoliosis. Progressive idiopathic early-onset scoliosis can be a life-threatening condition with negative effects on pulmonary function. Scoliosis that develops after 10 is referred to as adolescent idiopathic scoliosis. Screening adolescents without symptoms for scoliosis is of unclear benefit.
Definition
Scoliosis is defined as a three-dimensional deviation in the axis of a person's spine. Most instances, including the Scoliosis Research Society, define scoliosis as a Cobb angle of more than 10° to the right or left as the examiner faces the person, i.e. in the coronal plane.
Scoliosis has been described as a biomechanical deformity, the progression of which depends on asymmetric forces otherwise known as the Hueter–Volkmann Law.
Management
Our lack of understanding of the etiology and pathogenesis of scoliosis makes it difficult to manage. Scoliosis curves do not straighten out on their own. Many children have slight curves that do not need treatment. In these cases, the children grow up to lead a normal body posture by itself, even though their small curves never go away. If the patient is still growing and has a larger curve, it is important to monitor the curve for change by periodic examination and standing x-rays as needed. The rise in spinal abnormalities requires examination by a specialized physician, usually orthopedic surgeon or neurosurgeon, to determine if active treatment is needed. Although AIS normally does not cause health problems throughout development, the observable changes in appearance can have a substantial impact on teenagers, leading to quality-of-life concerns and, in extreme cases, emotional stress.
The traditional medical management of scoliosis is complex and is determined by the severity of the curvature and skeletal maturity, which together help predict the likelihood of progression.
The conventional options for children and adolescents are:
Physical therapy. Evidence suggests use of scoliosis specific exercises might prevent the progression of the curve along with possible bracing and surgery avoidance.
For adults, treatment usually focuses on relieving any pain:
Treatment for idiopathic scoliosis also depends upon the severity of the curvature, the spine's potential for further growth, and the risk that the curvature will progress. Mild scoliosis (less than 30° deviation) and moderate scoliosis (30–45°) can typically be treated conservatively with bracing in conjunction with scoliosis-specific exercises. Severe curvatures that rapidly progress may require surgery with spinal rod placement and spinal fusion. In all cases, early intervention offers the best results.
A specific type of physical therapy may be useful. Evidence to support its use, however, is weak. Low quality evidence suggests scoliosis-specific exercises (SSE) may be more effective than electrostimulation. Evidence for the Schroth method is insufficient to support its use. Significant improvement in function, vertebral angles and trunk asymmetries have been recorded following the implementation of Schroth method in terms of conservative management of scoliosis. Some other forms of exercise interventions have been lately used in clinical practice for the therapeutic management of scoliosis, such as global postural reeducation and the Klapp method.
Bracing
Bracing is normally done when the person has bone growth remaining and is, in general, implemented to hold the curve and prevent it from progressing to the point where surgery is recommended. In some cases with juveniles, bracing has reduced curves significantly, going from a 40° (of the curve, mentioned in length above) out of the brace to 18°. Braces are sometimes prescribed for adults to relieve pain related to scoliosis. Bracing involves fitting the person with a device that covers the torso; in some cases, it extends to the neck (example being the Milwaukee Brace).
The most commonly used brace is a TLSO, such as a Boston brace, a corset-like appliance that fits from armpits to hips and is custom-made from fiberglass or plastic. It is typically recommended to be worn 22–23 hours a day, and it applies pressure on the curves in the spine. The effectiveness of the brace depends not only on brace design and orthotist skill, but also on people's compliance and the amount of wear per day. An alternative form of brace is a nighttime-only brace, which is worn only at night whilst the child sleeps, and which overcorrects the deformity. Whilst nighttime braces are more convenient for children and families, it is unknown if the effectiveness of the brace is as good as conventional braces. The UK government has funded a large clinical trial (called the BASIS study) to resolve this uncertainty. The BASIS study is ongoing throughout the UK in all of the leading UK children's hospitals that treat scoliosis, with families encouraged to take part.
Indications for bracing: People who are still growing and who present with Cobb angles less than 20° should be closely monitored. People who are still growing and present with Cobb angles of 20 to 29° should be braced according to the risk of progression by considering age, Cobb angle increase over a six-month period, Risser sign, and clinical presentation. People who are still growing and present with Cobb angles greater than 30° should be braced. However, these are guidelines, and not every person will fit into this table.
For example, a person who is still growing with a 17° Cobb angle and significant thoracic rotation or flatback could be considered for nighttime bracing. On the opposite end of the growth spectrum, a 29° Cobb angle and a Risser sign three or four might not need to be braced because the potential for progression is reduced. The Scoliosis Research Society's recommendations for bracing include curves progressing to larger than 25°, curves presenting between 30 and 45°, Risser sign 0, 1, or 2 (an X-ray measurement of a pelvic growth area), and less than six months from the onset of menses in girls.
Evidence supports that bracing prevents worsening of disease, but whether it changes quality of life, appearance, or back pain is unclear.
Surgery
Surgery is usually recommended by orthopedists for curves with a high likelihood of progression (i.e., greater than 45–50° of magnitude), curves that would be cosmetically unacceptable as an adult, curves in people with spina bifida and cerebral palsy that interfere with sitting and care, and curves that affect physiological functions such as breathing.
Surgery is indicated by the Society on Scoliosis Orthopaedic and Rehabilitation Treatment (SOSORT) at 45–50° and by the Scoliosis Research Society (SRS) at a Cobb angle of 45°. SOSORT uses the 45–50° threshold as a result of the well-documented, plus or minus 5° measurement error that can occur while measuring Cobb angles.
Surgeons who specialize in spine surgery perform surgery for scoliosis. To completely straighten a scoliotic spine is usually impossible, but for the most part, significant corrections are achieved.
Anterior fusion: This surgical approach is through an incision at the side of the chest wall.
Posterior fusion: This surgical approach is through an incision on the back and uses metal instrumentation to correct the curve.
One or both of these surgical procedures may be needed. The surgery may be done in one or two stages and, on average, takes four to eight hours.
A new tethering procedure (anterior vertebral body tethering) may be appropriate for some patients.
Spine surgery can be painful and may also be associated with post-surgical pain. Different approaches for pain management are used in surgery, including epidural administration and systemic analgesia (also known as general analgesia). Epidural analgesia medication are often used surgically including combinations of local anesthetics and pain medications injected via an epidural injection. Evidence comparing different approaches for analgesia, side effects or benefits, and which approach results in greater pain relief and for how long after this type of surgery is of low to moderate quality.
In recent years, minimally invasive surgical (MIS) techniques have also been introduced in the treatment of scoliosis with the aim of reducing surgical trauma. These approaches seek to limit muscle dissection and soft-tissue damage by using smaller incisions and muscle-sparing techniques while still allowing spinal correction and instrumentation. The development of intraoperative imaging, navigation systems, and robotic assistance has facilitated the adoption of these techniques.
Prognosis
A 50-year follow-up study published in the Journal of the American Medical Association (2003) asserted that the lifelong physical health, including cardiopulmonary and neurological functions, and mental health of people with idiopathic scoliosis are comparable to those of the general population. Scoliosis that interferes with normal systemic functions is "exceptional" and "rare", and "untreated [scoliosis] people had similar death rates and were just as functional and likely to lead productive lives 50 years after diagnosis as people with normal spines." In an earlier University of Iowa follow-up study, 91% of people with idiopathic scoliosis displayed normal pulmonary function, and their life expectancy was found to be 2% more than that of the general population. Later (2006–) studies corroborate these findings, adding that they are "reassuring for the adult patient who has adolescent onset idiopathic scoliosis in approximately the 50–70° range." These modern landmark studies supersede earlier studies (e.g. Mankin-Graham-Schauk 1964) that did implicate moderate idiopathic scoliosis in impaired pulmonary function.
Generally, the prognosis of scoliosis depends on the likelihood of progression. The general rules of progression are larger curves carry a higher risk of progression than smaller curves, and thoracic and double primary curves carry a higher risk of progression than single lumbar or thoracolumbar curves. In addition, people not having yet reached skeletal maturity have a higher likelihood of progression (i.e., if the person has not yet completed the adolescent growth spurt).
Epidemiology
Scoliosis affects 2–3% of the United States population, or about five to nine million cases. A scoliosis (spinal column curve) of 10° or less affects 1.5–3% of individuals. The age of onset is usually between 10 years and 15 years (but can occur younger) in children and adolescents, making up to 85% of those diagnosed. This is due to rapid growth spurts during puberty when spinal development is most susceptible to genetic and environmental influences. Because female adolescents undergo growth spurts before postural musculoskeletal maturity, scoliosis is more prevalent among females.
Although fewer cases are present since using Cobb angle analysis for diagnosis, scoliosis remains significant, appearing in otherwise healthy children. Even though scoliosis is a disfigurement of the spine, it has been shown to influence the pulmonary function, balance while standing and stride execution in children. The impact of carrying backpacks on these three side effects has been broadly researched. Incidence of idiopathic scoliosis (IS) stops after puberty when skeletal maturity is attained, however further curvature may occur during late adulthood due to vertebral osteoporosis and weakened musculature.
Source: Wikipedia, The Free Encyclopedia · CC BY-SA 4.0
References
- Scoliosis — MedlinePlus, U.S. National Library of MedicineSource: MedlinePlus, National Library of Medicine Public domain (U.S. government work). Retrieved 2026-10-19.
- Scoliosis — Wikipedia, The Free EncyclopediaText from the Wikipedia article "Scoliosis" (CC BY-SA 4.0); excerpted. Licence. Retrieved 2026-10-19. Revision used.
Text above is quoted from the listed sources without changes to its meaning. Image credits and licences are shown with each image. Educational information only, not medical advice.
Related conditions
Educational overview, not medical advice. Treatment varies by person and location. Consult a qualified health professional for diagnosis or care. Content and model notes · Privacy information