
Measles
Measles is an infectious disease caused by a virus. It spreads easily from person to person. It causes a blotchy red rash. The rash often starts on the head and moves down the body. Other symptoms include:
- Fever
- Cough
- Runny nose
- Conjunctivitis (pink eye)
- Feeling achy and run down
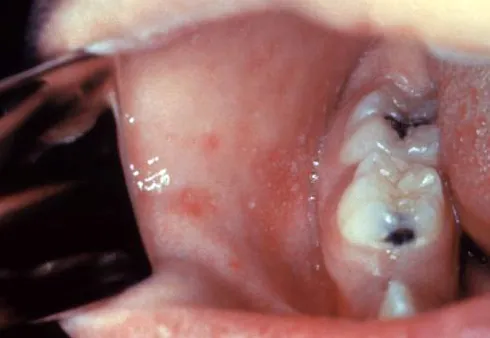
- Tiny white spots inside the mouth
Sometimes measles can lead to serious problems. There is no treatment for measles, but the measles-mumps-rubella (MMR) vaccine can prevent it.
"German measles", also known as rubella, is a completely different illness.
Centers for Disease Control and Prevention
Signs and symptoms
The initial symptoms of measles are non-specific, resembling a common cold - raised temperature, runny nose, sneezing, cough, and sore eyes (conjunctivitis). These symptoms begin 7–23 days (most commonly, 10–14 days) after exposure to an infected person. The fever may reach or exceed 104 °F (40 °C). After a couple more days, little white spots may appear inside the mouth (Koplik spots); they are short lived and may not be noticed. At this stage of infection a characteristic skin rash appears, initially on the face and behind the ears, spreading to the rest of the body.
Uncomplicated cases of measles typically improve within days of rash onset and resolve within 7–10 days. The virus is contagious from four days before to four days after the rash appears.
Because development of the rash and conjunctivitis requires a functional immune system, immunocompromised people may not be diagnosed as readily.
Complications
Immediate complications of measles are common, affecting approximately 30% of cases. Common complications are middle ear infections, conjunctivitis, severe diarrhea (leading to dehydration), and breathing problems such as croup and pneumonia.
Complications can be severe, such as encephalitis, deafness, blindness and rare but usually fatal subacute sclerosing panencephalitis (SSPE). In the US, the CDC estimates 1 out of every 5 unvaccinated people who get measles will need to be hospitalized; and that between 1 and 3 out of every 1,000 children with the disease will die of its complications. Mortality is worse in places with poor nutrition and poor healthcare - in parts of Africa, the case fatality rate is estimated up to 6% for settled populations, rising as high as 30% in refugee settlements. Pneumonia and encephalitis are the leading causes of death following measles.
Pregnancy
Measles during pregnancy can have serious consequences for both mother and child. Pregnant women infected with measles are significantly more likely to need hospitalisation and are at greater risk of pneumonia and death. There are also increased risks of miscarriage, premature delivery, and of babies having low birth weight,
Underlying mechanisms
Some complications are caused directly by the virus, while others are caused by viral suppression of the immune system.
The virus damages the membranes lining the respiratory tract (nose, throat and lungs), sometimes causing viral pneumonia but also making it easy for bacteria to cause secondary pneumonia and bronchitis. It can also damage the lining of the Eustachian tube, allowing bacteria to penetrate to and infect the middle ear (otitis media). Viral infection of the intestine leads to diarrhea, sometimes severe causing dehydration. In rare cases, the virus directly invades the central nervous system, triggering severe inflammatory responses or autoimmune demyelination, which can lead to post-infectious encephalitis.
A mechanism called "immune amnesia" (see below) underlies longer term consequences of measles. The virus targets the memory cells of the immune system; these are components of the adaptive immune system, providing the body with resistance to pathogens which have previously been encountered. Without these cells, the patient's body has little or no immunity to diseases which it had previously been immune to; the effect lasts for up to three years after the measles infection.
Those under 5 and over 20 are at higher risk for complications. Conditions which weaken or modify the immune response also increase risk for complications; these include pregnancy, malnutrition, hematologic cancer, HIV/AIDS, and use of immunosuppressive medication.
Immune amnesia
The measles virus can deplete previously acquired immune memory by killing cells that make antibodies, and thus weakens the immune system, opening the body up to potentially severe infections from other diseases. Suppression of the immune system by measles lasts up to three years and has been epidemiologically implicated in an increase in childhood mortality from other infectious diseases during this period. The measles vaccine contains an attenuated strain of the virus which does not deplete immune memory.
This suppression phenomenon, known as "immune amnesia", increases the risk of subsequent infections. Shortly after recovering from measles, there is a significant decrease in antibodies against other bacteria and viruses that patients may have acquired during their lifetimes prior to infection with the measles virus. Primate studies suggest that immune amnesia arises during infection when the virus destroys existing memory lymphocytes; after recovery, the body generates new memory lymphocytes which are specific to measles virus alone. This creates lasting immunity to measles re-infection, but destroys existing immunities to other diseases. Comparison of childhood mortality statistics from before and after the introduction of measles vaccination suggests that immune amnesia continues for 2–3 years following infection with the measles virus.
Cause
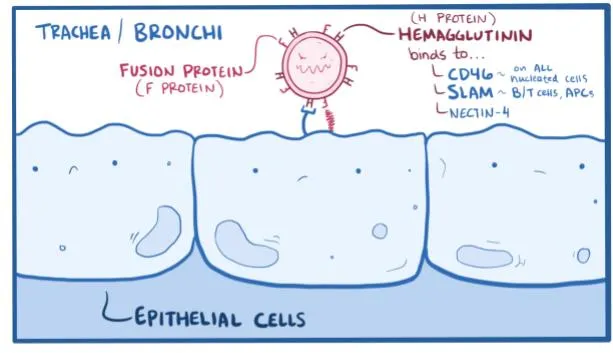
Measles is caused by the measles virus, a single-stranded, non-segmented, negative-sense, enveloped RNA virus of the genus Morbillivirus within the family Paramyxoviridae. It is related most closely to rinderpest, a cattle virus eradicated in 2001, and canine distemper, a mammalian disease that causes neurologic deterioration. There are 24 strains of measles virus divided into eight clades designated A-H.
Humans are the only natural hosts of the virus, and no other animal host is known to exist, although mountain gorillas are believed to be susceptible to the disease.
Risk factors for measles virus infection include immunodeficiency caused by HIV/AIDS, immunosuppression following receipt of an organ or a stem cell transplant, alkylating agents, or corticosteroid therapy, regardless of immunization status; and travel to areas where measles commonly occurs or contact with travelers from such an area. Very young children may be protected by antibodies acquired from their mother during pregnancy, but this immunity fades out a few weeks or months after birth.
Diagnosis
Symptoms of measles begin after an incubation period of about 10 days after exposure to the measles virus; they comprise fever, cough, runny nose, and conjunctivitis that worsen in severity over 4 days of appearing. Other diseases that may appear similar to measles include rubella, scarlet fever, erythema infectiosum, and roseola. Koplik spots are indicative of measles, but are hard to spot, transient and easily missed. The measles rash can easily be confused with other illnesses causing rashes. Laboratory confirmation is therefore strongly recommended, especially in areas where measles is uncommon.
Laboratory tests for measles comprise either detection of measles-specific IgM antibodies in a blood sample, or detection of measles virus RNA from throat, nasal or urine specimen by using the RT-PCR (reverse transcription polymerase chain reaction) assay. Both tests are most effective if samples are collected between 1 and 3 days after the onset of the measles rash.
Vaccination
Measles can be prevented in an individual by vaccination.
In places where measles is eliminated, it is generally recommended that children be immunized against measles using the MMR vaccine (measles, mumps, and rubella); the first dose at at 12–18 months of age with a second dose a few months later. In active outbreaks, an additional dose is recommended for infants between 6–11 months of age. The MMR vaccine is 95% effective for preventing measles after one dose if the vaccine is given to a child who is twelve months of age or older; if a second dose of the MMR vaccine is given, it will provide immunity in 97-99% of children. Mild reactions to the injection may include pain at the injection site, fever, and a rash; severe adverse reactions to vaccination are rare.
In places where measles is endemic, the World Health Organization recommends immunization at 9 months of age and again at 18 months of age. The vaccine is less effective when given earlier; the rate of antibody development when the initial dose is given at 9 months of age is 85-90%.
There have been false claims of an association between the MMR vaccine and autism; this incorrect concern has reduced the rate of vaccination and increased the number of cases of measles where immunization rates became too low to maintain herd immunity. Additionally, there have been false claims that measles infection protects against cancer.
In babies
During pregnancy, antibodies to measles are able to cross the placenta into fetal circulation, providing passive immunity to the newborn. This immunity wanes over the first 6 to 12 months of life.
Herd immunity
Herd immunity at population level may provide may provide a degree of protection. Because measles is highly infective, more than 95% of the population must be vaccinated in order to provide protection to the minority who are not immune. Individuals may nevertheless become infected if they encounter a person carrying the infection.
Post exposure
There are two treatment options available if a person without immunity is exposed to possible infection (post-exposure prophylaxis, PEP). The first (and preferable) option is a dose of the MMR vaccine, given within 72 hours of exposure. If this is contraindicated, injection or infusion of measles antibodies is effective up to the seventh day after exposure, but this does not confer permanent immunity.
Treatment
There is no specific antiviral treatment if measles develops. Instead the medications are generally aimed at treating secondary infections, maintaining good hydration with adequate fluids, and pain relief. Supportive treatment can include ibuprofen or paracetamol (acetaminophen) to reduce fever and pain and, if required, a fast-acting medication to dilate the airways for cough.
Vitamin A deficiency (VAD) is common in many low and middle income countries. A number of studies conducted conducted in countries where VAD is prevalent concluded that when children infected with measles were supplemented with vitamin A, there was a significant reduction in the severity of measles infection. The WHO and UNICEF recommend physician-administered vitamin A supplementation if this is a risk factor for an infected child.
Prognosis
Measles most commonly affects children, who have not acquired immunity through either vaccination or prior infection. Most people recover from measles, though in some cases, serious complications can occur; about 1 in 4 individuals will be hospitalized. Complications are more likely in children under age 5, adults over age 20, and pregnant people. Pneumonia is the most common fatal complication of measles infection and accounts for a large proportion of measles-related deaths.
Mortality in developed countries is relatively low. In England and Wales from 2020 to 2025 there were 16 deaths arising from 25,000 cases (.06%). In the United States, it is estimated that between 1 and 3 children will die per 1,000 cases (0.1–0.3%). In populations with high levels of malnutrition and a lack of adequate healthcare, mortality can be as high as 10%.
For people who have previously been infected or fully vaccinated, reinfection is rare but can occur in a milder form.
Epidemiology
Prior to the introduction of measles vaccine in 1963, measles was an endemic disease worldwide - meaning that it was constantly present, to a greater or lesser extent - in every part of the globe. It was estimated to cause approximately 135 million cases and 6 million deaths worldwide every year. With the introduction of vaccination programs, incidence of the disease was progressively reduced over the following decades, with laboratory confirmed cases reaching a low point of 159,000 in 2020, although there has been some resurgence subsequently. Because of regional under-reporting in areas with poor health systems, the estimated number of annual infections remains at 10 million.
In order to be considered measles-free, the WHO requires that a country must have no locally transmitted cases of the disease over a period of 12 months. During the 21st century, many countries achieved measles-free status; this includes much of Europe and the Western Pacific, as well as the entire region of the Americas. As of August 2026, a resurgence of measles (attributed to reduced vaccine coverage and vaccine hesitancy) has resulted in loss of measles-free status in a number of countries, including Canada (and by extension, the region of the Americas), the UK, Spain, and Austria.
Genetic analysis
Historically, genetic variants of the measles virus have been divided into 24 genotypes, grouped into 8 clades designated A to H. Despite this variation, there is only one serotype, meaning that immunity (once acquired) is effective against all clades. All vaccines are derived from laboratory cultures of Clade A. In 2003, 18 genotypes were in circulation globally; as of 2024 only two genotypes (B3 and D8) could be detected, indicating that vaccination programs had interrupted several chains of transmission.
Effects of the COVID-19 pandemic
Globally, reported measles cases decreased year-on year in the 21st century, but plateaued at 132,000 in 2016. In the following years, incidence increased to 874,000 by 2019. The increase was attributed to a failure in vaccination programs, principally in the poorest countries of the world. Cases dropped again in 2020, this credited to COVID-19 pandemic emergency measures such as lockdowns and social distancing which curtailed transmission of measles.
However the COVID-19 pandemic hindered vaccination campaigns in at least 68 countries. In February 2024, the World Health Organization warned that measles cases were increasing, and that more than half of the world was at risk of a measles outbreak due to disruptions of health systems and vaccination schedules during the years of COVID-19 pandemic.
In November 2024, the WHO and CDC reported that measles cases increased by 20% in 2023, primarily due to insufficient vaccine coverage in the world's poorest and conflict-affected regions, increasing from about 8.6 to 10.3 million cases. Nearly half of the major outbreaks and 64% of the individual cases occurred in Africa.
Global efforts
In 2000, the WHO established the Global Measles and Rubella Laboratory Network (GMRLN) to provide laboratory surveillance for measles, rubella, and congenital rubella syndrome. Before this, individual countries or regions were responsible for efforts to monitor and control measles. In 2001, the American Red Cross, CDC, UNICEF, the United Nations Foundation, and the WHO joined to form the Measles Initiative, aiming to reduce deaths in developing countries. This was later expanded to include the Gates Foundation and GAVI, and renamed the Measles & Rubella Partnership with the objective of eliminating both measles and rubella. As of 2026, this partnership has supported governments to deliver more than 3.86 billion doses of measles vaccine.
Europe
In England and Wales, though deaths from measles were uncommon, they averaged about 500 per year in the 1940s. Deaths diminished with the improvement of medical care in the 1950s, but the incidence of the disease did not reduce until vaccination was introduced in the late 1960s. Wider coverage was achieved in the 1980s with the measles, mumps and rubella, MMR vaccine.
In 2013–14, there were almost 10,000 cases in 30 European countries. Most cases occurred in unvaccinated individuals and over 90% of cases occurred in Germany, Italy, Netherlands, Romania, and United Kingdom. Between October 2014 and March 2015, a measles outbreak in the German capital of Berlin resulted in at least 782 cases.
In 2016, a record low of 5,273 cases in Europe were reported. 2017 saw an estimated measles vaccine coverage of 95% Europe-wide for the first dose and 90% for the second dose; nevertheless, regional gaps existed in coverage. Despite this, 2017 saw 21,315 cases, with 35 deaths. In 2018, reported cases in the region increased to 82,596 with 72 deaths; Ukraine had the most cases (53,218).
In 2019, the United Kingdom, Albania, the Czech Republic, and Greece lost their measles-free status due to ongoing and prolonged spread of the disease in these countries. In the first 6 months of 2019, 90,000 cases occurred in Europe.
A significant increase in measles cases in Europe occurred in 2024, with 127,350 being reported. This was the highest caseload in the region since 1997, representing a third of global measles cases. The major centre of the resurgent outbreak appeared to be Romania where 30,692 cases were reported.
Americas
As a result of widespread vaccination, the disease was declared eliminated from the Americas in 2016. However, there were cases again in 2017, 2018, 2019, 2020, and 2025 in this region.
Brazil
The spread of measles had been interrupted in Brazil in 2016, with the last-known case twelve months earlier in the state of Ceará.
Brazil won a measles elimination certificate by the Pan American Health Organization in 2016, but the Ministry of Health has proclaimed that the country has struggled to keep this certificate, since two outbreaks had already been identified in 2018, one in the state of Amazonas and another one in Roraima, in addition to cases in other states (Rio de Janeiro, Rio Grande do Sul, Pará, São Paulo and Rondônia), totaling 1,053 confirmed cases until 1 August 2018. In these outbreaks, and in most other cases, the contagion was related to the importation of the virus, especially from Venezuela. This was confirmed by the genotype of the virus (D8) that was identified, which is the same that circulates in Venezuela.
Canada
In 2025, Canada lost its measles-free status, recording 5,462 cases during the year. This is attributed to a drop in vaccine coverage from 90% in 2019 to 82% in 2022 and 2023.
United States
In the United States, measles affected approximately 3,000 people per million in the 1960s before the vaccine was available. With consistent widespread childhood vaccination, this figure fell to 13 cases per million by the 1980s, and to about 1 case per million by 2000.
In 1991, an outbreak of measles in Philadelphia was centered at the Faith Tabernacle Congregation, a faith-healing church that actively discouraged parishioners from vaccinating their children. Over 1400 people were infected with measles and nine children died.
Before immunization in the United States, between three and four million cases occurred each year. The United States was declared free of circulating measles in 2000, with 911 cases from 2001 to 2011. In 2014 the CDC said endemic measles, rubella, and congenital rubella syndrome had not returned to the United States. Occasional measles outbreaks persist, however, because of cases imported from abroad, of which more than half are the result of unvaccinated U.S. residents who are infected abroad and infect others upon return to the United States. The CDC continues to recommend measles vaccination throughout the population to prevent outbreaks like these.
In 2014, an outbreak was initiated in Ohio when two unvaccinated Amish men harboring asymptomatic measles returned to the United States from missionary work in the Philippines. Their return to a community with low vaccination rates led to an outbreak that rose to include a total of 383 cases across nine counties. Of the 383 cases, 340 (89%) occurred in unvaccinated individuals.
From 4 January, to 2 April 2015, there were 159 cases of measles reported to the CDC. Of those 159 cases, 111 (70%) were determined to have come from an earlier exposure in late December 2014. This outbreak was believed to have originated from the Disneyland theme park in California. The Disneyland outbreak was held responsible for the infection of 147 people in seven U.S. states as well as Mexico and Canada, the majority of which were either unvaccinated or had unknown vaccination status. Of the cases 48% were unvaccinated and 38% were unsure of their vaccination status. The initial exposure to the virus was never identified.
In 2015, a U.S. woman in Washington state died of pneumonia, as a result of measles. She was the first fatality in the U.S. from measles since 2003. The woman had been vaccinated for measles and was taking immunosuppressive drugs for another condition. The drugs suppressed the woman's immunity to measles, and the woman became infected with measles; she did not develop a rash, but contracted pneumonia, which caused her death.
In June 2017, the Maine Health and Environmental Testing Laboratory confirmed a case of measles in Franklin County. This instance marks the first case of measles in 20 years for the state of Maine. In 2018, one case occurred in Portland, Oregon, with 500 people exposed; 40 of them lacked immunity to the virus and were being monitored by county health officials as of 2 July 2018. There were 273 cases of measles reported throughout the United States in 2018, including an outbreak in Brooklyn with more than 200 reported cases from October 2018 to February 2019. The outbreak was tied with population density of the Orthodox Jewish community, with the initial exposure from an unvaccinated child that caught measles while visiting Israel.
A resurgence of measles occurred during 2019, which has been generally tied to parents choosing not to have their children vaccinated as most of the reported cases occurred in people 19 years old or younger. Cases were first reported in Washington state in January, with an outbreak of at least 58 confirmed cases most within Clark County, which has a higher rate of vaccination exemptions compared to the rest of the state; nearly one in four kindergartners in Clark did not receive vaccinations, according to state data. This led Washington state governor Jay Inslee to declare a state of emergency, and the state's congress to introduce legislation to disallow vaccination exemption for personal or philosophical reasons. In April 2019, New York Mayor Bill de Blasio declared a public health emergency because of "a huge spike" in cases of measles where there were 285 cases centred on the Orthodox Jewish areas of Brooklyn in 2018, while there were only two cases in 2017. There were 168 more in neighboring Rockland County. Other outbreaks occurred in Santa Cruz County and Butte County in California, and the states of New Jersey and Michigan. As of April 2019, there have been 695 cases of measles reported in 22 states. As of April 2019, this is the highest number of measles cases since measles was declared eliminated in 2000. From January, to December 2019, 1,282 individual cases of measles were confirmed in 31 states. This is the greatest number of cases reported in the US since 1992. Of the 1,282 cases, 128 of the people who got measles were hospitalized, and 61 reported having complications, including pneumonia and encephalitis. Following the end of the 2019 outbreak, reported cases fell to pre-outbreak levels: 13 cases in 2020, 49 cases in 2021, and 121 cases in 2022.
As of February 2025, an outbreak of measles is ongoing amongst unvaccinated communities in Texas and New Mexico. On 26 February, the first measles death since 2015 was reported to be that of an unvaccinated school-aged child in West Texas. The confirmed number of measles cases in this outbreak is 124 as of 26 February 2025, according to the Texas Department of Health Services. Most are in children ages 5–17. As of March 2025, the CDC has recorded 483 confirmed cases across 20 states, 2 deaths and 70 hospitalized. This exceeds the entire 2024 total that was only 285.
Southeast Asia
In the Vietnamese measles epidemic in spring of 2014, an estimated 8,500 measles cases were reported as of 19 April, with 114 fatalities; as of 30 May, 21,639 suspected measles cases had been reported, with 142 measles-related fatalities. In the Naga Self-Administered Zone in a remote northern region of Myanmar, at least 40 children died during a measles outbreak in August 2016 that was probably caused by lack of vaccination in an area of poor health infrastructure. Following the 2019 Philippines measles outbreak, 23,563 measles cases have been reported in the country with 338 fatalities. A measles outbreak also happened among the Malaysian Orang Asli sub-group of Batek people in the state of Kelantan from May 2019, causing the deaths of 15 from the tribe. In 2024, a measles outbreak was declared in the Bangsamoro region in the Philippines with at least 592 cases and 3 deaths.
Australia
Measles is a notifiable disease, which is required to be reported to the National Notifiable Diseases Surveillance System. The NNDSS portal shows statistics on measles since 1991, showing that the high of 4,794 cases in 1994 dropped to 10 by 2005 after a significant public health campaign initiated in 1998. Numbers have varied since then, reducing to zero during the COVID-19 pandemic in Australia in 2021, but rising to 181 in 2025.
Samoa
A measles outbreak in Samoa in late 2019 has over 5,700 cases of measles and 83 deaths, out of a Samoan population of 200,000. Over three percent of the population were infected, and a state of emergency was declared from 17 November to 7 December. A vaccination campaign brought the measles vaccination rate from 31 to 34% in 2018 to an estimated 94% of the eligible population in December 2019.
Africa
The Democratic Republic of the Congo and Madagascar have reported the highest numbers of cases in 2019. However, cases have decreased in Madagascar as a result of nationwide emergency measles vaccine campaigns. As of August 2019 outbreaks were occurring in Angola, Cameroon, Chad, Nigeria, South Sudan and Sudan.
Madagascar
An outbreak of measles in 2018 has resulted in well beyond 115,000 cases and over 1,200 deaths.
Democratic Republic of Congo
An outbreak of measles with nearly 5,000 deaths and 250,000 infections occurred in 2019, after the disease spread to all the provinces in the country. Most deaths were among children under five years of age. The World Health Organization (WHO) has reported this as the world's largest and fastest-moving epidemic.
Source: Wikipedia, The Free Encyclopedia · CC BY-SA 4.0
References
- Measles — MedlinePlus, U.S. National Library of MedicineSource: MedlinePlus, National Library of Medicine Public domain (U.S. government work). Retrieved 2026-10-19.
- Measles — Wikipedia, The Free EncyclopediaText from the Wikipedia article "Measles" (CC BY-SA 4.0); excerpted. Licence. Retrieved 2026-10-19. Revision used.
Text above is quoted from the listed sources without changes to its meaning. Image credits and licences are shown with each image. Educational information only, not medical advice.
Related conditions
Educational overview, not medical advice. Treatment varies by person and location. Consult a qualified health professional for diagnosis or care. Content and model notes · Privacy information