
Epilepsy
Also called: Seizure disorder
Epilepsy is a brain disorder that causes people to have recurring seizures. The seizures happen when clusters of nerve cells, or neurons, in the brain send out the wrong signals. People may have strange sensations and emotions or behave strangely. They may have violent muscle spasms or lose consciousness.
Epilepsy has many possible causes, including illness, brain injury, and abnormal brain development. In many cases, the cause is unknown.
Doctors use brain scans and other tests to diagnose epilepsy. It is important to start treatment right away. There is no cure for epilepsy, but medicines can control seizures for most people. When medicines are not working well, surgery or implanted devices such as vagus nerve stimulators may help. Special diets can help some children with epilepsy.
NIH: National Institute of Neurological Disorders and Stroke
Signs and symptoms
Epilepsy is characterized by a long-term tendency to experience recurrent, unprovoked seizures. They may vary widely in their presentation depending on the affected brain regions, age of onset, and type of epilepsy.
Seizures
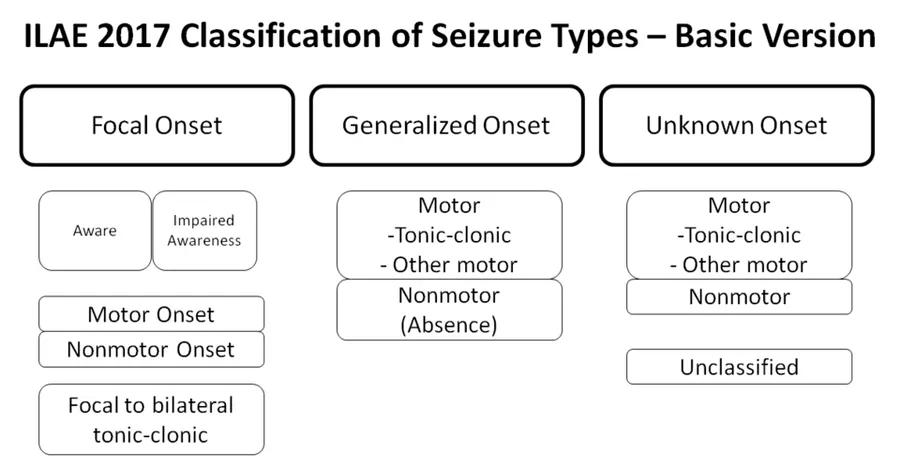
According to the 2025 classification by the International League Against Epilepsy (ILAE), seizures are grouped into four main classes: focal, generalized, unknown (whether focal or generalized), and unclassified.
Focal seizures
Focal seizures originate in one area of the brain and may involve localized or distributed networks. For a given seizure type, the site of onset tends to be consistent across episodes. Once initiated, the seizure may remain localized or spread to adjacent areas, and in some cases, may propagate to the opposite hemisphere (contralateral spread).
They are further classified based on the state of consciousness during the episode:
Focal preserved consciousness seizure: the person remains aware and responsive.
Focal impaired consciousness seizure: awareness or responsiveness are affected.
Experiences known as auras often precede focal seizures. The seizures can include sensory (visual, hearing, or smell), psychic, autonomic, and motor phenomena depending on which part of the brain is involved. Muscle jerks may start in a specific muscle group and spread to surrounding muscle groups, a pattern known as a Jacksonian march. Automatisms, or non-consciously generated activities, may occur; these may be simple repetitive movements like smacking the lips or more complex activities such as attempts to pick up something. Some focal seizures can evolve into focal-to-bilateral tonic-clonic seizures, where abnormal brain activity spreads to both hemispheres.
Generalized seizures
Generalized seizures originate at a specific point within, and quickly spread across both hemispheres through interconnected brain networks. Although the spread is rapid, the onset may appear asymmetric in some cases. These seizures typically impair consciousness from the outset and can take several forms, including:
Generalized tonic–clonic seizures, often with an initial tonic phase followed by clonic jerking;
Absence seizures, which may present with eye blinking or automatisms;
Other generalized seizures, a category that includes tonic, clonic, myoclonic, atonic seizures and epileptic spasms.
Tonic–clonic seizures are among the most recognizable seizure types, typically involving sudden loss of consciousness, stiffening (tonic phase), and rhythmic jerking (clonic phase) of the limbs. This form of seizure (whether focal to bilateral, generalized, or of unknown onset) is associated with the highest risk of injury, medical complications, and sudden unexpected death in epilepsy (SUDEP).
Myoclonic seizures involve sudden, brief muscle jerks, which may affect specific muscle groups or the whole body. They can cause falls and injury. Absence seizures are characterized by brief lapses in awareness, sometimes accompanied by subtle movements such as blinking or slight head turning. The person typically recovers immediately afterward without confusion. Atonic seizures involve a sudden loss of muscle tone, often resulting in falls.
Triggers and reflex seizures
Certain external or internal factors may increase the likelihood of a seizure in individuals with epilepsy. Common triggers include sleep deprivation, stress, fever, illness, menstruation, alcohol, and certain medications. These do not cause seizures by themselves, but lower the threshold in people who are already susceptible.
A small subset of individuals have reflex epilepsy, in which seizures are reliably provoked by specific stimuli. These reflex seizures account for about 6% of epilepsy cases. Common triggers include flashing lights (photosensitive epilepsy), sudden sounds, or specific cognitive tasks such as reading or performing calculations. In some epilepsy syndromes, seizures occur more frequently during sleep or upon awakening.
Seizure clusters
Seizure clusters are multiple seizures occurring over a short period of time, with incomplete recovery between events. They are distinct from status epilepticus, though the two may overlap. Definitions vary across studies, but seizure clusters are typically described as two or more seizures within 24 hours or a noticeable increase in seizure frequency over a person's usual baseline. Estimates of their prevalence range widely (from 5% to 50% of people with epilepsy) largely due to differing definitions and populations studied. Seizure clusters are more common in individuals with drug-resistant epilepsy, high baseline seizure frequency, or certain epilepsy syndromes. They are associated with increased emergency care utilization, worse quality of life, impaired psychosocial functioning, and possibly elevated risk of mortality.
Postictal state
After the active portion of a seizure (the ictal state) there is typically a period of recovery during which there is confusion, referred to as the postictal state, before a normal level of consciousness returns, lasting minutes to days. This period is marked by confusion, headache, fatigue, or speech and motor disturbances. Some may experience Todd's paralysis, a transient focal weakness. Postictal psychosis occurs in approximately 2% of individuals with epilepsy, particularly after clusters of generalized tonic–clonic seizures.
Causes
Epilepsy can result from a wide range of genetic and acquired factors, and in many cases, both play a role. Acquired causes include serious traumatic brain injury, stroke, brain tumors, and central nervous system infections. Despite advances in diagnostic tools, no clear cause is identified in approximately 50% of cases. The distribution of causes often varies with age. Epilepsies associated with genetic, congenital, or developmental conditions are more common in children, while epilepsy related to stroke or tumors is more frequently seen in older adults.
Seizures may also occur as a direct response to acute health conditions such as stroke, head trauma, metabolic disturbances, or toxic exposures. These are known as acute symptomatic seizures and are distinct from epilepsy, which involves a recurrent tendency to have unprovoked seizures over time.
The International League Against Epilepsy (ILAE) classifies the causes of epilepsy into six broad categories: structural, genetic, infectious, metabolic, immune, and unknown. These categories are not mutually exclusive, and more than one may apply in an individual case.
Structural
Structural causes of epilepsy refer to abnormalities in the anatomy of the brain that increase the risk of seizures. These may be acquired (such as from a stroke, traumatic brain injury, brain tumor, or central nervous system infection) or developmental and genetic in origin, as seen in conditions like focal cortical dysplasia or certain congenital brain malformations. A major example is mesial temporal sclerosis (MTS), a common cause of temporal lobe epilepsy. In terms of temporal lobe epilepsy, another cause can also be what are called the large conductance, Ca2+-activated K+ (BKCa) ion channels in the neurons, or BK channel. This is due to how the loss-of-function BKCa channels can contribute to neuronal hyperexcitability. This can also cause tonic-clonic seizures as well.
Traumatic brain injury is estimated to cause between 6% and 20% of epilepsy cases, depending on severity, mechanism, and study population. Mild brain injury increases the risk about two-fold, while severe brain injury increases the risk seven-fold. In those who have experienced a high-powered gunshot wound to the head, the risk is about 50%. Stroke is a major cause of epilepsy, particularly in older adults. Approximately 6% to 10% of individuals who experience a stroke develop epilepsy, most often within the first few years after the event. The risk is highest following severe strokes that involve cortical regions, especially in cases of intracerebral hemorrhage. Brain tumors are implicated in approximately 4% of epilepsy cases, with seizures occurring in nearly 30% of individuals with intracranial neoplasms.
In clinical practice, a structural cause is typically identified through neuroimaging (such as MRI), which reveals an abnormality that plausibly accounts for the individual's seizure semiology and EEG findings. The lesion must be epileptogenic, meaning that it is capable of generating seizures. Infections like encephalitis or brain abscess may lead to permanent structural damage, increasing the risk of epilepsy even after the infection resolves.
Structural damage can also result from perinatal brain injury, such as hypoxic-ischemic encephalopathy, especially in low- and middle-income countries where access to prenatal and neonatal care may be limited. When seizures are linked to a clearly defined structural lesion, epilepsy surgery may be considered, particularly in individuals whose seizures do not respond to medication.
Genetics
Genetic causes of epilepsy are those in which a person's genes directly contribute to the development of seizures. This includes cases where a specific mutation has been identified, as well as situations where the family history and clinical features strongly suggest a genetic basis, even if no known mutation is found. In the updated classification by the ILAE, the term genetic replaces the older term idiopathic.
Genetic factors can contribute either directly or by increasing vulnerability to other causes. Around 1–2% of cases are caused by a single gene defect, while most are due to a combination of multiple genes and environmental influences. Many of the genes known to play a role in epilepsy affect how brain cells send electrical signals, especially those involved in ion channels, receptors or signaling proteins. Extensive screening have failed to identify many single gene variants of large effect. More recent exome and genome sequencing studies have begun to reveal a number of de novo mutations that are responsible for some epileptic encephalopathies, including CHD2 and SYNGAP1 and DNM1, GABBR2, FASN and RYR3.
Some genetic disorders, including phakomatoses such as tuberous sclerosis complex and Sturge–Weber syndrome are strongly associated with epilepsy.
Infectious
Infectious causes include infections of the central nervous system that directly affect brain tissue and lead to long-term seizure susceptibility. Examples include herpes simplex encephalitis, which carries a high risk of developing epilepsy, and neurocysticercosis, a major preventable cause of epilepsy in endemic regions. Other infections such as cerebral malaria, toxoplasmosis, and toxocariasis.
Immune
Immune causes include conditions like autoimmune encephalitis, in which the immune system attacks brain tissue, often presenting with seizures. Certain autoimmune epilepsies are associated with specific autoantibodies, including those against the NMDA receptor, LGI1 and CASPR2. These cases often present with rapid-onset, difficult-to-treat seizures.
Celiac disease has also been associated with epilepsy in rare syndromic forms, such as the triad of epilepsy, cerebral calcifications, and celiac disease.
Metabolic
Metabolic causes of epilepsy include metabolic disorders that disrupt the brain's normal function. In rare cases, epilepsy may result from inborn errors of metabolism, such as porphyria, mitochondrial diseases, urea cycle disorders or glucose transporter type 1 (GLUT1) deficiency. These often present early in life and may be associated with developmental delays, movement disorders and other neurological symptoms.
Seizures can also occur in the context of acquired metabolic disturbances, such as hypoglycemia, hyponatremia or hypocalcemia, often in cases of acute symptomatic seizures, not epilepsy.
Some forms of malnutrition, particularly in low- and middle-income countries, have been associated with a higher risk of epilepsy, although it remains unclear whether the relationship is causal or due to other contributing factors.
Unknown
Unknown causes of epilepsy are cases where no clear structural, genetic, infectious, immune or metabolic origin can be identified despite thorough evaluation. A substantial proportion of epilepsy cases still fall into this group, particularly in regions with limited access to advanced testing.
Diagnosis
The diagnosis of epilepsy is primarily clinical, based on a thorough evaluation of the person's history, seizure features, and risk of recurrence. Diagnostic tests such as electroencephalograms and neuroimaging can support the diagnosis. Clinicians must also distinguish epileptic seizures from other conditions that can mimic them and determine whether the event was provoked by an acute, reversible cause or if it suggests a long-term tendency for unprovoked seizures.
Definition
According to the International League Against Epilepsy (ILAE), a diagnosis of epilepsy can be made when any one of the following criteria is met:
The ILAE also introduced the concept of resolved epilepsy, which applies to individuals who are past the typical age range for an age-dependent syndrome, or who have remained seizure-free for at least 10 years, including the last 5 years without medication.
This 2014 practical definition built upon the broader 2005 conceptual framework, which defined epilepsy as a disorder involving an enduring predisposition to generate epileptic seizures. The updated criteria incorporated recurrence risk and reflected the realities of clinical decision-making. While widely adopted in clinical settings, other definitions, such as the traditional "two unprovoked seizures" rule still used by the World Health Organization, remain appropriate in epidemiology and public health contexts, provided they are clearly stated. The 2014 revision also changed its terminology, referring to epilepsy as a disease rather than a disorder.
Classification
Once epilepsy is diagnosed, the ILAE recommends a three-level framework to guide further classification and management:
Identify the seizure type, based on clinical features and EEG (e.g., focal aware seizure, generalized absence)
Determine the epilepsy type, such as focal, generalized, combined, or unknown
Identify an epilepsy syndrome, if applicable
Not all levels can always be determined; in some cases, only the seizure type is identifiable. The etiology (whether structural, genetic, infectious, metabolic, immune, or unknown) should be considered at each stage of classification, as it often influences treatment and prognosis.
The classification of epilepsies has evolved over time. Earlier systems emphasized seizure location and used terms such as "partial" or "cryptogenic," which have been replaced in the modern framework. The current system, introduced in 2017, was proposed to reflect advances in neuroimaging, genetics, and in the clinical understanding of the condition.
Syndromes
An epilepsy syndrome is a specific diagnosis based on a combination of features, including seizure types, age of onset, EEG patterns, imaging findings, and associated symptoms or comorbidities. In many cases, a known genetic or structural cause may also support the diagnosis.
Some syndromes are self-limited and age-dependent, such as childhood absence epilepsy, juvenile myoclonic epilepsy, and self-limited epilepsy with centrotemporal spikes, and typically respond well to treatment or remit with age. In contrast, more severe syndromes fall under the category of developmental and epileptic encephalopathies (DEEs). These include Lennox–Gastaut syndrome, West syndrome, Rasmussen syndrome and Dravet syndrome, which typically present in early childhood with drug-resistant seizures and are associated with significant neurodevelopmental impairments.
Some epilepsy syndromes do not yet fit neatly within current etiological categories, particularly when no definitive cause has been identified. In many cases, a genetic cause is presumed based on age of onset, family history, and electroclinical features, even if no mutation has been found.
Tests
The diagnostic evaluation of epilepsy begins with a detailed clinical history, supported by eyewitness accounts and, when available, video recordings, to confirm whether the reported event was a seizure and distinguish it from common mimics such as non-epileptic seizures.
Following clinical evaluation, selected tests including a sleep study may be used to rule out acute causes and seizure mimics. A 12-lead electrocardiogram (ECG) is recommended for all individuals presenting with a first seizure, to screen for cardiac arrhythmias and other cardiovascular conditions that may resemble epilepsy. Blood tests may be performed to identify metabolic disturbances such as hypoglycemia, electrolyte imbalances, or renal and hepatic dysfunction, particularly in acute settings.
Once epilepsy is suspected, electroencephalography (EEG) is used to support the diagnosis. A routine EEG may include activation techniques such as hyperventilation or photic stimulation. However, a normal EEG does not rule out epilepsy. When initial EEG findings are inconclusive, prolonged monitoring techniques such as ambulatory or video EEG may be necessary, including sleep-deprived recordings.
Neuroimaging, usually with magnetic resonance imaging (MRI), is recommended to detect structural causes of epilepsy. If MRI is contraindicated or unavailable, computed tomography (CT) may be considered.
Additional tests may be guided by clinical context. Genetic testing may be considered in individuals with early-onset epilepsy, developmental delay or features of a known genetic epilepsy syndrome. Testing for neuronal antibodies may be appropriate in suspected cases of autoimmune encephalitis, particularly when seizures are new-onset, progressive or treatment-resistant. Metabolic testing may be pursued in infants or children with unexplained epilepsy, especially when developmental regression or multisystem involvement is present.
Serum prolactin may occasionally be measured after a suspected seizure, particularly to help distinguish epileptic seizures from non-epileptic events. While it can be elevated following certain seizure types, the test lacks sufficient sensitivity and specificity and is not recommended for routine use.
Differential diagnosis
Several conditions can resemble epileptic seizures and are collectively referred to as non-epileptic seizures. Common mimics include fainting (syncope), psychogenic non-epileptic seizures (PNES), transient ischemic attacks, migraine, narcolepsy, and various sleep or movement disorders. In children, events such as reflux, breath-holding spells, parasomnias and others may resemble seizures.
Psychogenic non-epileptic seizures (PNES) are involuntary episodes that resemble epileptic seizures but are not associated with abnormal electrical discharges. They are classified as functional neurological disorders and are typically associated with psychological distress or trauma. Studies suggest that approximately 20% of individuals referred to epilepsy centers are diagnosed with PNES, and up to 10% of these individuals also have coexisting epilepsy. Differentiating between the two can be difficult and often requires prolonged video EEG monitoring.
Misdiagnosis remains a significant concern in epilepsy. Reported rates vary widely, from 2% to 71%, depending on factors such as clinical setting, patient population, diagnostic criteria and physician expertise.
Prevention
Although many causes of epilepsy are not preventable, several known risk factors are modifiable. Perinatal care can lower the risk of epilepsy in infants. Vaccination programs, especially against neurotropic infections such as measles and meningitis, play a key role in preventing epilepsy caused by central nervous system infections. In low- and middle-income countries, neurocysticercosis remains a major preventable cause of epilepsy, which can be reduced through improved sanitation and food safety. Eliminating or reducing risk factors for seizures in older adults such as inactivity, smoking, diabetes, high blood pressure, and excessive alcohol consumption have been suggested as strategies to help prevent epilepsy in older adults.
Complications
Epilepsy can lead to a range of medical, psychological, and social complications, particularly when seizures are frequent or uncontrolled. One of the most serious risks is injury during a seizure, including falls, burns, or accidents while driving, swimming, or operating machinery. The risk of drowning is significantly increased in people with epilepsy, especially those with poor seizure control.
People with epilepsy are at greater risk for mental health conditions, including depression, anxiety, and social isolation. These challenges are often compounded by stigma, employment difficulties, and driving restrictions. In children, epilepsy, especially when drug-resistant, can interfere with cognitive development and academic performance.
A rare but serious complication is sudden unexpected death in epilepsy (SUDEP), which is most often associated with uncontrolled generalized tonic–clonic seizures, particularly during sleep.
Management
The primary goals of epilepsy management are to control seizures, minimize treatment side effects, and optimize quality of life. Management strategies are individualized based on the type of seizures or epilepsy syndrome, the underlying cause when known, the person's age and comorbidities, and their preferences and life circumstances.
Supporting people's self-management of their condition may be useful. In drug-resistant cases, different management options may be considered, including special diets, the implantation of a neurostimulator, or neurosurgery.
First aid and acute management of seizures
During a generalized tonic–clonic seizure, the primary goals are to ensure safety and prevent injury. The following steps should be taken:
Stay calm and remove any potential hazards from the area. Clear the space of sharp objects, furniture, or anything that might cause injury.
If the person is standing, gently guide them to the ground to avoid a fall.
Position the person on their side and into the recovery position, which helps keep the airway clear and reduces the risk of choking. If possible, place something soft (e.g., a jacket or cushion) under their head to prevent injury.
Do not restrain their movements or attempt to hold them down. Do not put anything in their mouth, as this may cause harm.
If the seizure lasts longer than 5 minutes or if multiple seizures occur without full recovery in between, it is important to call for emergency medical assistance immediately, as it is considered a medical emergency known as status epilepticus.
Convulsive status epilepticus requires immediate medical attention to prevent serious complications. In a community setting (such as at home or in the ambulance), first-line treatment includes the administration of benzodiazepines. If the person has an individualized emergency management plan, which may have been developed with healthcare providers and outlines personalized treatment steps (such as the use of buccal midazolam or rectal diazepam), this plan should be followed immediately. In hospital, intravenous lorazepam is preferred.
If seizures continue after the first dose of benzodiazepine, emergency medical services should be contacted, and further doses can be given. For ongoing seizures, levetiracetam, phenytoin, or sodium valproate may be used as second-line treatments, with levetiracetam preferred for its quicker action and fewer side effects.
Most institutions have a preferred pathway or protocol to be used in a seizure emergency like status epilepticus. These protocols have been found to be effective in reducing time to delivery of treatment.
Medications
The primary treatment for epilepsy involves the use of antiseizure medications (ASMs), which aim to control seizures while minimizing side effects. Treatment plans should be individualized, taking into account the seizure type, epilepsy syndrome, patient age, sex, comorbidities, lifestyle factors, and the potential for drug interactions.
First-line treatment for most individuals with epilepsy is monotherapy with a single ASM. For many people with epilepsy, seizure control is achieved with a single medication, but some may require combination therapy if seizures are not well-controlled with monotherapy.
There are a number of medications available including phenytoin, carbamazepine and valproate. Evidence suggests that these drugs are similarly effective for both focal and generalized seizures, although their side-effect profiles vary. Controlled release carbamazepine appears to work as well as immediate release carbamazepine, and may have fewer side effects. In the UK, carbamazepine or lamotrigine are recommended as first-line treatments for focal seizures, with levetiracetam and valproate used as second-line treatments due to concerns about cost and side effects. Valproate is the first-line choice for generalized seizures, while lamotrigine is used as second-line. For absence seizures, ethosuximide or valproate are recommended, with valproate also being effective for myoclonic and tonic–clonic seizures.
Controlled-release formulations of carbamazepine may be preferred in some cases, as they appear to be equally effective as immediate-release carbamazepine but may have fewer side effects. Once a person's seizures are well-controlled on a specific treatment, it is generally not necessary to routinely check medication blood levels, unless there are concerns about side effects or toxicity.
In low- and middle-income countries (LMICs), the management of epilepsy is often hindered by limited access to medications, diagnostic tools, and specialized care. While phenytoin and carbamazepine are commonly used as first-line treatments due to their availability and low cost, newer drugs like levetiracetam and lamotrigine may not be accessible. Additionally, surgical options and advanced therapies, such as vagus nerve stimulation or resective surgery, are typically inaccessible due to high costs and lack of infrastructure.
The least expensive anticonvulsant is phenobarbital at around US$5 a year. The World Health Organization gives it a first-line recommendation in LMICs and it is commonly used in these countries. Access, however, may be difficult as some countries label it as a controlled drug.
Adverse effects from medications are reported in 10% to 90% of people, depending on how and from whom the data is collected. Most adverse effects are dose-related and mild. Some examples include mood changes, sleepiness, or an unsteadiness in gait. Certain medications have side effects that are not related to dose such as rashes, liver toxicity, or suppression of the bone marrow. Up to a quarter of people stop treatment due to adverse effects. Some medications are associated with birth defects when used in pregnancy. Many of the common used medications, such as valproate, phenytoin, carbamazepine, phenobarbital, and gabapentin have been reported to cause increased risk of birth defects, especially when used during the first trimester. Despite this, treatment is often continued once effective, because the risk of untreated epilepsy is believed to be greater than the risk of the medications. Among the antiepileptic medications, levetiracetam and lamotrigine seem to carry the lowest risk of causing birth defects.
Gradually stopping medications may be considered by a physician in some people who have been seizure-free for two to four years. Around a third of patients have a recurrence, most often during the first six months. Stopping is possible in about 70% of children and 60% of adults. Measuring medication levels is not generally needed in those whose seizures are well controlled.
Surgery
Epilepsy surgery is a treatment option for individuals with drug-resistant epilepsy, typically defined as the failure of at least two appropriately chosen and tolerated antiseizure medications. Surgery is most effective in cases of focal epilepsy, where seizures originate from a specific area of the brain that can be safely removed.
Epilepsy surgery remains underutilized worldwide and is often reserved for individuals whose condition has reached an advanced or chronic stage. This evaluation, conducted in specialized epilepsy centers, includes seizure classification, long-term video EEG monitoring, high-resolution MRI with epilepsy-specific protocols, neuropsychological assessment, and sometimes functional imaging or invasive monitoring. Early referral improves the likelihood of successful outcomes and avoids prolonged periods of unnecessary disability.
The primary goal of epilepsy surgery is to achieve seizure freedom, but even when that is not possible, palliative procedures that significantly reduce seizure frequency can lead to meaningful improvements in quality of life and development, particularly in children. Studies suggest that 60-70% of individuals with drug-resistant focal epilepsy experience a substantial reduction in seizures following surgery.
Common procedures include anterior temporal lobe resection, which often involves removal of the hippocampus in cases of mesial temporal lobe epilepsy, as well as lesionectomy for tumors or cortical dysplasia, and lobectomy for larger seizure foci. In cases where resection is not possible, procedures such as corpus callosotomy may help reduce the severity and spread of seizures. In addition to traditional resective techniques, minimally invasive approaches such as MRI-guided laser interstitial thermal therapy (LITT) have gained traction as safer alternatives in select cases, particularly where reducing cognitive impact and recovery time is a priority. In many cases, antiseizure medications can be tapered following successful surgery, though long-term monitoring remains essential. Surgical treatment is not limited to adults. A 2023 systematic review found that early surgery in children under 3 years with drug-resistant epilepsy can result in meaningful seizure reduction or freedom when other treatments have failed.
Neuromodulation
Neurotherapy or Neuromodulation therapies, including vagus nerve stimulation (VNS), deep brain stimulation (DBS), Neuromodulation through Radiotherapy (e.g. Leksell Gamma Knife) and responsive neurostimulation (RNS), are treatment options for individuals with drug-resistant epilepsy who are not candidates for resective surgery, or for whom previous surgery has not resulted in seizure freedom. These neurotherapies aim to reduce seizure frequency and severity by delivering controlled electrical stimulation to targeted neural circuits.
Diet
Dietary therapy, particularly the ketogenic diet (high-fat, low-carbohydrate, adequate-protein), is a non-pharmacological treatment option used primarily in children with drug-resistant epilepsy. Evidence suggests that children on a classical ketogenic diet may be up to three times more likely to achieve seizure freedom and up to six times more likely to experience a ≥50% reduction in seizure frequency compared to those receiving standard care. Modified versions of the diet, such as the modified Atkins diet, are better tolerated but may be less effective. In adults, the ketogenic diet has shown limited evidence of achieving seizure freedom, though it may increase the likelihood of seizure reduction. However, further research is necessary.
It is typically supervised by a multidisciplinary team, including neurologists and dietitians, due to its restrictive nature and potential side effects, such as vomiting, constipation and diarrhoea. Regular monitoring of nutritional status, blood parameters, and growth is recommended. It is unclear why this diet works. The diet leads to an increased elevation of plasma decanoic acid and ketones. However, some research is giving the indication that it may be the decanoic acid that is anti-convulsant.
A gluten-free diet has been proposed in rare cases of epilepsy associated with celiac disease and occipital calcifications, though evidence is limited and based on small case series.
Adjunctive and complementary therapies
There is moderate-quality evidence supporting the use of psychological interventions, such as cognitive behavioral therapy (CBT), relaxation techniques, and self-management training, alongside standard treatment. These approaches may improve quality of life, emotional wellbeing, and treatment adherence; however, evidences targeting seizure control are uncertain. Avoidance therapy consists of minimizing or eliminating triggers. For example, those who are sensitive to light may have success with using a small television, avoiding video games, or wearing dark glasses. Biofeedback, particularly EEG-based operant conditioning, has shown preliminary benefit in some people with drug-resistant epilepsy. However, these methods are considered adjunctive and are not recommended as standalone treatments.
Cannabidiol (CBD) has shown benefit as an add-on therapy in certain severe childhood epilepsies. A purified form of CBD was approved by the U.S. FDA in 2018 and by the European Medicines Agency (EMA) in 2020 for the treatment of Dravet syndrome, Lennox–Gastaut syndrome, and tuberous sclerosis complex.
Regular physical activity is generally considered safe and may have beneficial effects on seizure frequency, mood, and overall wellbeing. While evidence remains limited, some studies suggest that moderate exercise can reduce seizure burden in certain individuals. Seizure response dogs have been trained to assist individuals during or after seizures by providing physical support or alerting others. Although anecdotal reports claim that some dogs can anticipate seizures, there is no conclusive scientific evidence supporting the consistent ability of dogs to predict seizures before they occur.
Various forms of alternative medicine, including acupuncture, routine vitamins, and yoga, have no reliable evidence to support their use in epilepsy. Melatonin, as of 2016, is insufficiently supported by evidence. The trials were of poor methodological quality and it was not possible to draw any definitive conclusions.
Prognosis
Epilepsy is generally considered a chronic neurological condition. Its long-term course can vary widely depending on factors such as seizure type, underlying cause, and response to treatment. Although epilepsy is not typically "cured," in many cases it may be considered resolved. According to the ILAE, epilepsy is considered to be resolved in individuals who have been seizure-free for at least 10 years, with no antiseizure medications for the last 5 of those years.
Approximately 60–70% of individuals with epilepsy achieve good seizure control with appropriate antiseizure medications, and many can maintain long-term remission. Outcomes vary by epilepsy type and etiology. Early treatment response is one of the strongest predictors of long-term outcome, with poor early control correlating with lower chances of remission. Several factors, such as structural brain abnormalities, comorbid developmental disorders, or a high frequency of seizures at onset, have been associated with worse outcomes, although findings are not always consistent.
Epilepsy disproportionately affects low- and middle-income countries, where nearly 80% of the global epilepsy population resides. In these countries, up to 75% of individuals with epilepsy do not receive the treatment they need. Untreated epilepsy is associated with elevated risk of injury, psychiatric comorbidities, and early death, including sudden unexpected death in epilepsy (SUDEP).
Cognition
Cognitive impairment frequently accompanies epilepsy, although it is difficult to determine to what extant it is caused by the epilepsy itself. This is because observed cognitive decline could be a result of the cause of the epilepsy (e.g. epilepsy caused by mesial temporal sclerosis), or be secondary to the epilepsy (e.g. brain damage from falling due to a seizure, or impairment from pharmacological or surgical treatment of the epilepsy).
In the majority of people who achieve seizure control, there is no associated progressive cognitive decline. However, severe intractable epilepsy is associated with negative cognitive effects. Due to its variability, it is unclear whether any given case of epilepsy will lead to cognitive decline, but a few points are noted:
Epilepsy is associated with increased risk for Alzheimer's disease (and vice-versa).
Longer seizures cause more damage than shorter seizures.
Progressive thinning of the cerebral cortex occurs with recurring seizures.
Mortality
People with epilepsy may have a higher risk of premature death compared to those without the condition. This risk is estimated to be between 1.6 and 4.1 times greater than that of the general population. The greatest increase in mortality from epilepsy is among the elderly. Those with epilepsy due to an unknown cause have a relatively low increase in risk.
Mortality is often related to the underlying cause of the seizures, status epilepticus, suicide, trauma, and sudden unexpected death in epilepsy (SUDEP). Death from status epilepticus is primarily due to an underlying problem rather than missing doses of medications. The risk of suicide is between two and six times higher in those with epilepsy; the cause of this is unclear. SUDEP appears to be partly related to the frequency of generalized tonic-clonic seizures and accounts for about 15% of epilepsy-related deaths; it is unclear how to decrease its risk. Risk factors for SUDEP include nocturnal generalized tonic-clonic seizures, seizures, sleeping alone and medically intractable epilepsy.
In the United Kingdom, it is estimated that 40–60% of deaths are possibly preventable. In the developing world, many deaths are due to untreated epilepsy leading to falls or status epilepticus.
Epidemiology
Epilepsy is one of the most common serious neurological disorders, affecting approximately 50 million people globally as of 2021, with the majority living in low- and middle-income countries. The point prevalence of active epilepsy is generally reported between 5 and 7 per 1,000 people, while lifetime prevalence is slightly higher, typically between 6 and 9 per 1,000. Both prevalence and incidence are higher in low-income regions. The annual incidence of epilepsy (the rate of new diagnoses each year) is estimated at 50 to 70 new cases per 100,000 people globally, based on population studies. Rates are significantly higher in low- and middle-income countries, and, within high-income countries, higher incidence has also been observed among lower socioeconomic groups and some ethnic minorities.
Epilepsy can develop at any age, but its incidence is highest in early infancy and in older adults, following a bimodal distribution. In high-income countries, the incidence peaks during the first year of life, declines during adulthood, and rises again in people over age 85. The increase in older adults is associated with age-related conditions such as stroke, brain tumors, and neurodegenerative diseases. In low- and middle-income countries, incidence more often peaks in older children and young adults. Epilepsy is slightly more common in males than females, a difference that may be associated with risk factor exposure and underreporting in women in some regions due to sociocultural factors.
Epilepsy is responsible for an estimated 13 million disability-adjusted life years (DALYs) worldwide each year, with the majority of this burden falling on individuals in low-resource settings where access to diagnosis and treatment remains limited.
Source: Wikipedia, The Free Encyclopedia · CC BY-SA 4.0
References
- Epilepsy — MedlinePlus, U.S. National Library of MedicineSource: MedlinePlus, National Library of Medicine Public domain (U.S. government work). Retrieved 2026-10-19.
- Epilepsy — Wikipedia, The Free EncyclopediaText from the Wikipedia article "Epilepsy" (CC BY-SA 4.0); excerpted. Licence. Retrieved 2026-10-19. Revision used.
Text above is quoted from the listed sources without changes to its meaning. Image credits and licences are shown with each image. Educational information only, not medical advice.
Related conditions
Educational overview, not medical advice. Treatment varies by person and location. Consult a qualified health professional for diagnosis or care. Content and model notes · Privacy information