
Deep vein thrombosis
Also called: DVT, Venous thromboembolism
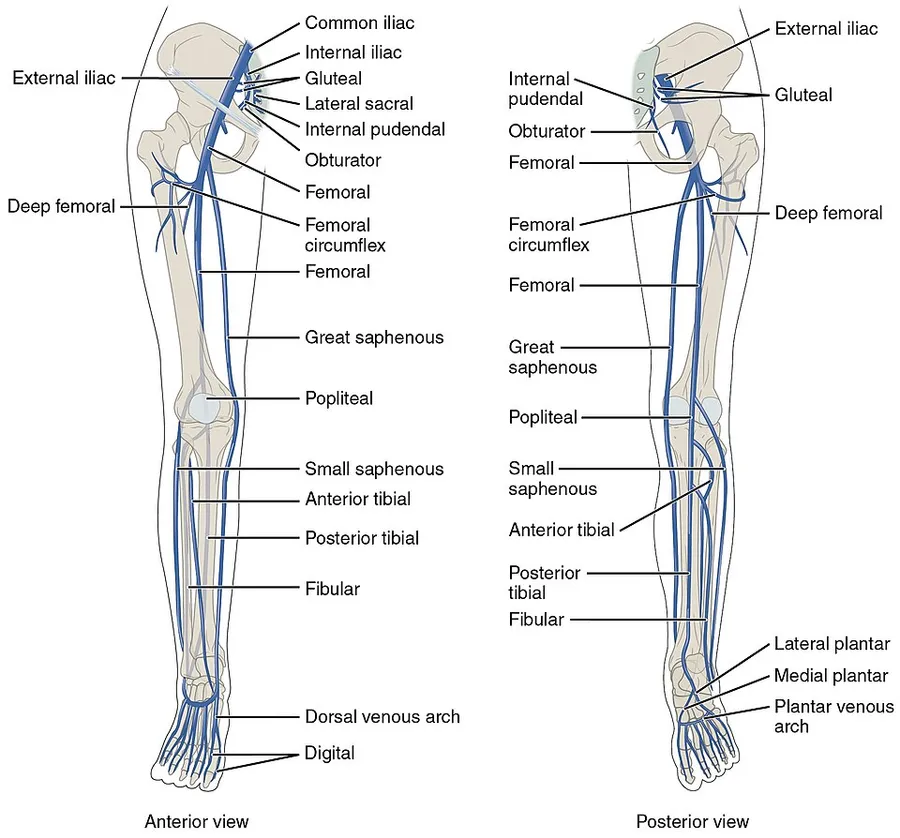
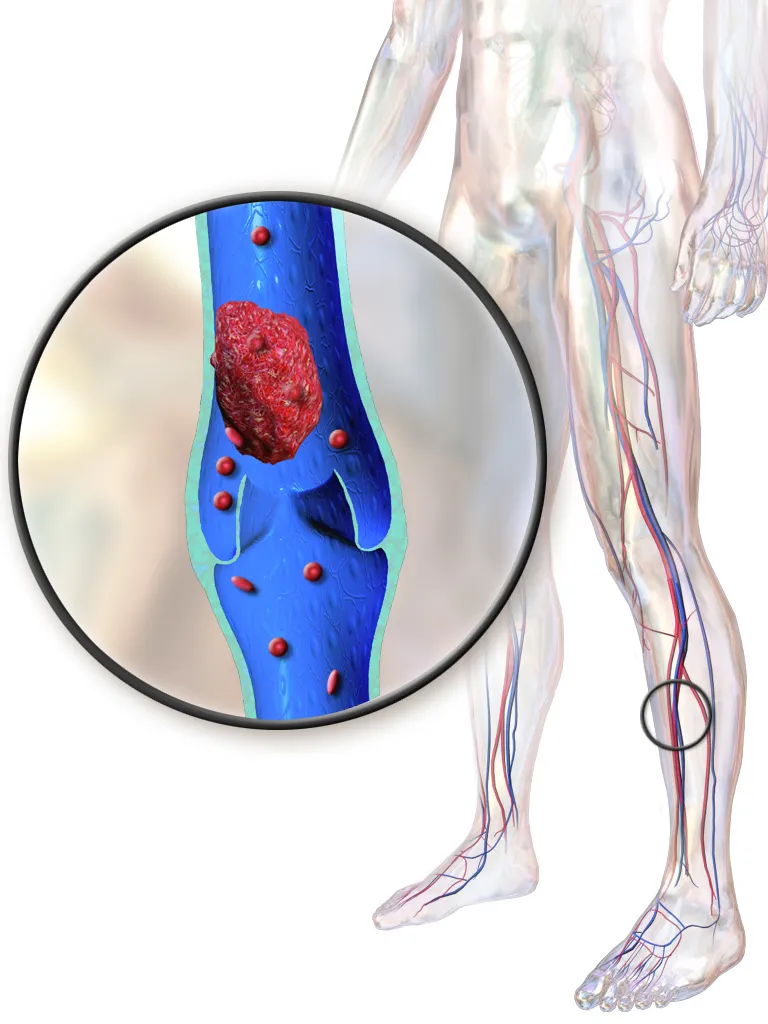
Deep vein thrombosis, or DVT, is a blood clot that forms in a vein deep in the body. Most deep vein clots occur in the lower leg or thigh. If the vein swells, the condition is called thrombophlebitis. A deep vein thrombosis can break loose and cause a serious problem in the lung, called a pulmonary embolism.
Sitting still for a long time can make you more likely to get a DVT. Some medicines and disorders that increase your risk for blood clots can also lead to DVTs. Common symptoms are:
- Warmth and tenderness over the vein
- Pain or swelling in the part of the body affected
- Skin redness
Treatment includes medicines to ease pain and inflammation, break up clots and keep new clots from forming. Keeping the affected area raised and applying moist heat can also help. If you are taking a long car or plane trip, take a break, walk or stretch your legs and drink plenty of liquids.
Signs and symptoms
Symptoms classically affect a leg and typically develop over hours or days, though they can develop suddenly or over a matter of weeks. The legs are primarily affected, with 4–10% of DVT occurring in the arms. Despite the signs and symptoms being highly variable, the typical symptoms are pain, swelling, and redness. However, these symptoms might not manifest in the lower limbs of those unable to walk. In those who are able to walk, DVT can reduce one's ability to do so. The pain can be described as throbbing and can worsen with weight-bearing, prompting one to bear more weight with the unaffected leg.
Additional signs and symptoms include tenderness, pitting edema (see image), dilation of surface veins, warmth, discoloration, a "pulling sensation", and even cyanosis (a blue or purplish discoloration) with fever. DVT can also exist without causing any symptoms. Signs and symptoms help in determining the likelihood of DVT, but they are not used alone for diagnosis.
At times, DVT can cause symptoms in both arms or both legs, as with bilateral DVT. Rarely, a clot in the inferior vena cava can cause both legs to swell. Superficial vein thrombosis, also known as superficial thrombophlebitis, is the formation of a blood clot (thrombus) in a vein close to the skin. It can co-occur with DVT and can be felt as a "palpable cord". Migratory thrombophlebitis (Trousseau's syndrome) is a noted finding in those with pancreatic cancer and is associated with DVT.
Potential complications
A pulmonary embolism (PE) occurs when a blood clot from a deep vein (a DVT) detaches from a vein (embolizes), travels through the right side of the heart, and becomes lodged as an embolus in a pulmonary artery that supplies deoxygenated blood to the lungs for oxygenation. Up to one-fourth of PE cases are thought to result in sudden death. When not fatal, PE can cause symptoms such as sudden onset shortness of breath or chest pain, coughing up blood (hemoptysis), and fainting (syncope). The chest pain can be pleuritic (worsened by deep breaths) and can vary based upon where the embolus is lodged in the lungs. An estimated 30–50% of those with PE have detectable DVT by compression ultrasound.
A rare and massive DVT that causes significant obstruction and discoloration (including cyanosis) is phlegmasia cerulea dolens. It is life-threatening, limb-threatening, and carries a risk of venous gangrene. Phlegmasia cerulea dolens can occur in the arm but more commonly affects the leg. If found in the setting of acute compartment syndrome, an urgent fasciotomy is warranted to protect the limb. Superior vena cava syndrome is a rare complication of arm DVT.
DVT is thought to be able to cause a stroke in the presence of a heart defect. This is called a paradoxical embolism because the clot abnormally travels from the pulmonary circuit to the systemic circuit while inside the heart. The defect of a patent foramen ovale is thought to allow clots to travel through the interatrial septum from the right atrium into the left atrium.
Differential diagnosis
In most suspected cases, DVT is ruled out after evaluation. Cellulitis is a frequent mimic of DVT, with its triad of pain, swelling, and redness. Symptoms concerning for DVT are more often due to other causes, including cellulitis, ruptured Baker's cyst, hematoma, lymphedema, and chronic venous insufficiency. Other differential diagnoses include tumors, venous or arterial aneurysms, connective tissue disorders, superficial vein thrombosis, muscle vein thrombosis, and varicose veins.
Classification
DVT and PE are the two manifestations of the cardiovascular disease venous thromboembolism (VTE). VTE can occur as DVT only, DVT with PE, or PE only. About two-thirds of VTE manifests as DVT only, with one-third manifesting as PE with or without DVT. VTE, along with superficial vein thrombosis, are common types of venous thrombosis.
DVT is classified as acute when the clots are developing or have recently developed, whereas chronic DVT persists for more than 28 days. Differences between these two types of DVT can be seen with ultrasound. An episode of VTE after an initial one is classified as recurrent. Bilateral DVT refers to clots in both limbs while unilateral means only a single limb is affected.
DVT in a leg above the knee is termed proximal DVT (proximal). DVT in a leg below the knee is termed distal DVT (distal), also called calf DVT when affecting the calf, and has limited clinical significance compared to proximal DVT. Calf DVT makes up about half of DVTs. Iliofemoral DVT is described as involving either the iliac, or common femoral vein; elsewhere, it has been defined as involving at a minimum the common iliac vein, which is near the top of the pelvis.
DVT can be classified as provoked and unprovoked. For example, DVT that occurs in association with cancer or surgery can be classified as provoked. However, the European Society of Cardiology in 2019 urged for this dichotomy to be abandoned to encourage more personalized risk assessments for recurrent VTE. The distinction between these categories is not always clear.
Causes
Traditionally, the three factors of Virchow's triad—venous stasis, hypercoagulability, and changes in the endothelial blood vessel lining—contribute to VTE and were used to explain its formation. More recently, inflammation has been identified as playing a clear causal role. Other related causes include activation of immune system components, the state of microparticles in the blood, the concentration of oxygen, and possible platelet activation. Various risk factors contribute to VTE, including genetic and environmental factors, though many with multiple risk factors never develop it.
Acquired risk factors include the strong risk factor of older age, which alters blood composition to favor clotting. Previous VTE, particularly unprovoked VTE, is a strong risk factor. A leftover clot from a prior DVT increases the risk of a subsequent DVT. Major surgery and trauma increase risk because of tissue factor from outside the vascular system entering the blood. Minor injuries, lower limb amputation, hip fracture, and long bone fractures are also risks. In orthopedic surgery, venous stasis can be temporarily provoked by a cessation of blood flow as part of the procedure. Inactivity and immobilization contribute to venous stasis, as with orthopedic casts, paralysis, sitting, long-haul travel, bed rest, hospitalization, catatonia, and in survivors of acute stroke. Conditions that involve compromised blood flow in the veins are May–Thurner syndrome, where a vein of the pelvis is compressed, and venous thoracic outlet syndrome, which includes Paget–Schroetter syndrome, where compression occurs near the base of the neck.
Infections, including sepsis, COVID-19, HIV, and active tuberculosis, increase risk. Chronic inflammatory diseases and some autoimmune diseases, such as inflammatory bowel disease, systemic sclerosis, Behçet's syndrome, primary antiphospholipid syndrome, and systemic lupus erythematosus (SLE) increase risk. SLE itself is frequently associated with secondary antiphospholipid syndrome.
Cancer can grow in and around veins, causing venous stasis. It can also stimulate higher levels of tissue factor. Cancers of the blood, lung, pancreas, brain, stomach, and bowel are associated with high VTE risk. Solid tumors such as adenocarcinomas can contribute to both VTE and disseminated intravascular coagulation. In severe cases, this can lead to simultaneous clotting and bleeding. Chemotherapy treatment also increases risk. Obesity increases the potential of blood to clot, as does pregnancy. In the postpartum, placental tearing releases substances that favor clotting. Oral contraceptives and hormonal replacement therapy increase the risk through various mechanisms, including altered blood coagulation protein levels and reduced fibrinolysis.
Dozens of genetic risk factors have been identified, and they account for approximately 50 to 60% of the variability in VTE rates. As such, family history of VTE is a risk factor for a first VTE. Factor V Leiden, which makes factor V resistant to inactivation by activated protein C, mildly increases VTE risk by about three times. Deficiencies of three proteins that normally prevent blood from clotting—protein C, protein S, and antithrombin—contribute to VTE. These deficiencies in antithrombin, protein C, and protein S are rare but strong, or moderately strong, risk factors. They increase risk by about 10 times. Having a non-O blood type roughly doubles VTE risk. Non-O blood type is common globally, making it an important risk factor. Individuals without O blood type have higher blood levels of von Willebrand factor and factor VIII than those with O blood type, increasing the likelihood of clotting. Those homozygous for the common fibrinogen gamma gene variant rs2066865 have about a 1.6 times higher risk of VTE. The genetic variant prothrombin G20210A, which increases prothrombin levels, increases risk by about 2.5 times. Additionally, approximately 5% of people have been identified with a background genetic risk comparable to the factor V Leiden and prothrombin G20210A mutations.
Blood alterations including dysfibrinogenemia, low free protein S, activated protein C resistance, homocystinuria, hyperhomocysteinemia, high fibrinogen levels, high factor IX levels, and high factor XI levels are associated with increased risk. Other associated conditions include heparin-induced thrombocytopenia, catastrophic antiphospholipid syndrome, paroxysmal nocturnal hemoglobinuria, nephrotic syndrome, chronic kidney disease, polycythemia vera, essential thrombocythemia, intravenous drug use, and smoking.
Some risk factors influence the location of DVT within the body. In isolated distal DVT, the profile of risk factors appears distinct from proximal DVT. Transient factors, such as surgery and immobilization, appear to dominate, whereas thrombophilias and age do not seem to increase risk. Common risk factors for having an upper extremity DVT include having an existing foreign body (such as a central venous catheter, a pacemaker, or a triple-lumen PICC line), cancer, and recent surgery.
Diagnosis
A clinical probability assessment using the Wells score (see column in the table below) to determine if a potential DVT is "likely" or "unlikely" is typically the first step of the diagnostic process. The score is used in suspected first lower extremity DVT (without any PE symptoms) in primary care and outpatient settings, including the emergency department. The numerical result (possible score −2 to 9) is most commonly grouped into either "unlikely" or "likely" categories. A Wells score of two or more means DVT is considered "likely" (about a 28% chance), while those with a lower score are considered "unlikely" to have DVT (about a 6% chance). In those unlikely to have DVT, a diagnosis is excluded by a negative D-dimer blood test. In people with likely DVT, ultrasound is the standard imaging used to confirm or exclude a diagnosis. Imaging is also needed for hospital inpatients with suspected DVT and those initially categorized as unlikely to have DVT but who have a positive D-dimer test.
While the Wells score is the predominant and most studied clinical prediction rule for DVT, it does have drawbacks. The Wells score requires a subjective assessment regarding the likelihood of an alternate diagnosis and performs less well in the elderly and those with a prior DVT. The Dutch Primary Care Rule has also been validated for use. It contains only objective criteria but requires obtaining a D-dimer value. With this prediction rule, three points or less means a person is at low risk for DVT. A result of four or more points indicates an ultrasound is needed. Instead of using a prediction rule, experienced physicians can make a DVT pre-test probability assessment using clinical assessment and gestalt, but prediction rules are more reliable.
Compression ultrasonography for suspected deep vein thrombosis is the standard diagnostic method, and it is highly sensitive for detecting an initial DVT. A compression ultrasound is considered positive when the vein walls of normally compressible veins do not collapse under gentle pressure. Clot visualization is sometimes possible, but is not required. Three compression ultrasound scanning techniques can be used, with two of the three methods requiring a second ultrasound some days later to rule out the diagnosis. Whole-leg ultrasound is the option that does not require a repeat ultrasound, but proximal compression ultrasound is frequently used because distal DVT is only rarely clinically significant. Ultrasound methods including duplex and color flow Doppler can be used to characterize the clot further and Doppler ultrasound is especially helpful in the non-compressible iliac veins.
CT scan venography, MRI venography, or a non-contrast MRI are also diagnostic possibilities. The gold standard for judging imaging methods is contrast venography, which involves injecting a peripheral vein of the affected limb with a contrast agent and taking X-rays, to reveal whether the venous supply has been obstructed. Because of its cost, invasiveness, availability, and other limitations, this test is rarely performed.
Management
Treatment for DVT is warranted when the clots are either proximal, distal, and symptomatic, or upper extremity and symptomatic. Providing anticoagulation, or blood-thinning medicine, is the typical treatment after patients are checked to make sure they are not subject to bleeding. However, treatment varies depending upon the location of DVT. For example, in cases of isolated distal DVT, ultrasound surveillance (a second ultrasound after 2 weeks to check for proximal clots), might be used instead of anticoagulation. Although, those with isolated distal DVT at a high risk of VTE recurrence are typically anticoagulated as if they had proximal DVT. Those at low risk of recurrence might receive a four- to six-week course of anticoagulation, lower doses, or no anticoagulation at all. In contrast, those with proximal DVT should receive at least 3 months of anticoagulation.
Some anticoagulants can be taken by mouth, and these oral medicines include warfarin (a vitamin K antagonist), rivaroxaban (a factor Xa inhibitor), apixaban (a factor Xa inhibitor), dabigatran (a direct thrombin inhibitor), and edoxaban (a factor Xa inhibitor). Other anticoagulants cannot be taken by mouth. These parenteral (non-oral) medicines include low-molecular-weight heparin (LMWH), fondaparinux, and unfractionated heparin. Some oral medicines are sufficient when taken alone, while others require an additional parenteral blood thinner. Rivaroxaban and apixaban are the typical first-line medicines, and they are sufficient when taken orally. Rivaroxaban is taken once daily, and apixaban is taken twice daily. Warfarin, dabigatran, and edoxaban require the use of a parenteral anticoagulant to initiate oral anticoagulant therapy. When warfarin is initiated for VTE treatment, a 5-day minimum of a parenteral anticoagulant together with warfarin is given, which is followed by warfarin-only therapy. Warfarin is taken to maintain an international normalized ratio (INR) of 2.0–3.0, with 2.5 as the target. The benefit of taking warfarin declines as the duration of treatment extends, and the risk of bleeding increases with age. Periodic INR monitoring is not necessary when first-line direct oral anticoagulants are used. Overall, anticoagulation therapy is complex, and many circumstances can affect how these therapies are managed.
The duration of anticoagulation therapy (whether it will last 4 to 6 weeks, 6 to 12 weeks, 3 to 6 months, or indefinitely) is a key factor in clinical decision making. When proximal DVT is provoked by surgery or trauma a 3-month course of anticoagulation is standard. When a first VTE is proximal DVT that is either unprovoked or associated with transient non-surgical risk factor, low-dose anticoagulation beyond 3 to 6 months might be used. In those with an annual risk of VTE in excess of 9%, as after an unprovoked episode, extended anticoagulation is a possibility. Those who finish warfarin treatment after idiopathic VTE with an elevated D-dimer level show an increased risk of recurrent VTE (about 9% vs about 4% for normal results), and this result might be used in clinical decision making. Thrombophilia test results rarely play a role in the length of treatment.
Treatment for acute leg DVT is suggested to continue at home for uncomplicated DVT instead of hospitalization. Factors that favor hospitalization include severe symptoms or additional medical issues. Early walking is suggested over bedrest. Graduated compression stockings—which apply higher pressure at the ankles and a lower pressure around the knees can be trialed for symptomatic management of acute DVT symptoms, but they are not recommended for reducing the risk of post-thrombotic syndrome, as the potential benefit of using them for this goal "may be uncertain". Nor are compression stockings likely to reduce VTE recurrence. They are, however, recommended in those with isolated distal DVT.
If someone decides to stop anticoagulation after an unprovoked VTE instead of being on lifelong anticoagulation, aspirin can be used to reduce the risk of recurrence. It is only about 33% as effective as anticoagulation in preventing recurrent VTE. Statins have also been investigated for their potential to reduce recurrent VTE rates, with some studies suggesting effectiveness.
Investigations for cancer
An unprovoked VTE might signal the presence of an unknown cancer, as it is an underlying condition in up to 10% of unprovoked cases. A thorough clinical assessment is needed and should include a physical examination, a review of medical history, and universal cancer screening done in people of that age. A review of prior imaging is considered worthwhile, as is "reviewing baseline blood test results including full blood count, renal and hepatic function, PT and APTT." It is not recommended practice to obtain tumor markers or a CT of the abdomen and pelvis in asymptomatic individuals. NICE recommends that further investigations are unwarranted in those without relevant signs or symptoms.
Interventions
Thrombolysis is the injection of an enzyme into the veins to dissolve blood clots, and while this treatment has been proven effective against the life-threatening emergency clots of stroke and heart attacks, randomized controlled trials have not established a net benefit in those with acute proximal DVT. Drawbacks of catheter-directed thrombolysis (the preferred method of administering the clot-busting enzyme) include a risk of bleeding, complexity, and the cost of the procedure. Although, while anticoagulation is the preferred treatment for DVT, thrombolysis is a treatment option for those with the severe DVT form of phlegmasia cerula dorens (bottom left image) and in some younger patients with DVT affecting the iliac and common femoral veins. Of note, a variety of contraindications to thrombolysis exist. In 2020, NICE kept their 2012 recommendations that catheter-directed thrombolysis should be considered in those with iliofemoral DVT who have "symptoms lasting less than 14 days, good functional status, a life expectancy of 1 year or more, and a low risk of bleeding."
A mechanical thrombectomy device can remove DVT clots, particularly in acute iliofemoral DVT (DVT of the major veins in the pelvis), but there is limited data on its efficacy. It is usually combined with thrombolysis, and sometimes, temporary IVC filters are placed to protect against PE during the procedure. Catheter-directed thrombolysis with thrombectomy against iliofemoral DVT has been associated with a reduction in the severity of post-thrombotic syndrome at an estimated cost-effectiveness ratio of about $138,000 per gained QALY. Phlegmasia cerulea dolens might be treated with catheter-directed thrombolysis and/or thrombectomy.
In DVT in the arm, the first (topmost) rib can be surgically removed as part of the typical treatment when the DVT is due to thoracic outlet syndrome or Paget–Schroetter syndrome. This treatment involves initial anticoagulation followed by thrombolysis of the subclavian vein and staged first rib resection to relieve the thoracic outlet compression and prevent recurrent DVT.
The placement of an inferior vena cava filter (IVC filter) is possible when either the standard treatment for acute DVT, anticoagulation, is absolutely contraindicated (not possible), or if someone develops a PE despite being anticoagulated. However, a 2020 NICE review found "little good evidence" for their use. A 2018 study associated IVC filter placement with a 50% reduction in PE, a 70% increase in DVT, and an 18% increase in 30 day mortality when compared to no IVC placement. Other studies including a systematic review and meta-analysis did not find a difference in mortality with IVC placement. If someone develops a PE despite being anticoagulated, care should be given to optimize anticoagulation treatment and address other related concerns before considering IVC filter placement.
Field of medicine
Patients with a history of DVT might be managed by primary care, general internal medicine, hematology, cardiology, vascular surgery, or vascular medicine. Patients suspected of having an acute DVT are often referred to the emergency department for evaluation. Interventional radiology is the specialty that typically places and retrieves IVC filters, and vascular surgery might do catheter directed thrombosis for some severe DVTs.
Prevention
For the prevention of blood clots in the general population, incorporating leg exercises while sitting down for long periods, or having breaks from a sitting position and walking around, having an active lifestyle, and maintaining a healthy body weight are recommended. Walking increases blood flow through the leg veins. Excess body weight is modifiable, unlike most risk factors, and interventions or lifestyle modifications that help someone who is overweight or obese lose weight reduce DVT risk. Avoiding both smoking and a Western pattern diet are thought to reduce risk. Statins have been investigated for primary prevention (prevention of a first VTE), and the JUPITER trial, which used rosuvastatin, has provided some tentative evidence of effectiveness. Of the statins, rosuvastatin appears to be the only one with the potential to reduce VTE risk. If so, it appears to reduce risk by about 15%. However, the number needed to treat to prevent one initial VTE is about 2000, limiting its applicability.
Hospital (non-surgical) patients
Acutely ill hospitalized patients are suggested to receive a parenteral anticoagulant, although the potential net benefit is uncertain. Critically ill hospitalized patients are recommended to either receive unfractionated heparin or low-molecular weight heparin instead of foregoing these medicines.
After surgery
Major orthopedic surgery—total hip replacement, total knee replacement, or hip fracture surgery—has a high risk of causing VTE. If prophylaxis is not used after these surgeries, symptomatic VTE has about a 4% chance of developing within 35 days. Following major orthopedic surgery, a blood thinner or aspirin is typically paired with intermittent pneumatic compression, which is the preferred mechanical prophylaxis over graduated compression stockings.
Options for VTE prevention in people following non-orthopedic surgery include early walking, mechanical prophylaxis, and blood thinners (low-molecular-weight heparin and low-dose unfractionated heparin), depending on the risk of VTE, risk of major bleeding, and the person's preferences. After low-risk surgeries, early and frequent walking is the best preventive measure.
Pregnancy
The risk of VTE is increased in pregnancy by about four to five times because of a more hypercoagulable state that protects against fatal postpartum hemorrhage. Preventive measures for pregnancy-related VTE were suggested by the American Society of Hematology in 2018. Warfarin, a common vitamin K antagonist, can cause birth defects and is not used for prevention during pregnancy.
Travelers
Travelling "is an often cited yet relatively uncommon" cause of VTE. Suggestions for at-risk long-haul travelers include calf exercises, frequent walking, and aisle seating in airplanes to ease walking. Graduated compression stockings have sharply reduced the levels of asymptomatic DVT in airline passengers, but the effect on symptomatic DVT, PE, or mortality is unknown, as none of the individuals studied developed these outcomes. However, graduated compression stockings are not suggested for long-haul travelers (>4 hours) without risk factors for VTE. Likewise, neither aspirin nor anticoagulants are suggested in the general population undertaking long-haul travel. Those with significant VTE risk factors undertaking long-haul travel are suggested to use either graduated compression stockings or LMWH for VTE prevention. If neither of these two methods are feasible, then aspirin is suggested.
Prognosis
DVT is most frequently a disease of older age that occurs in the context of nursing homes, hospitals, and active cancer. It is associated with a 30-day mortality rate of about 6%, with PE being the cause of most of these deaths. Proximal DVT is frequently associated with PE, unlike distal DVT, which is rarely if ever associated with PE. Around 56% of those with proximal DVT also have PE, although a chest CT is not needed simply because of the presence of DVT. If proximal DVT is left untreated, in the following 3 months approximately half of people will experience symptomatic PE.
Another frequent complication of proximal DVT, and the most frequent chronic complication, is post-thrombotic syndrome, where individuals have chronic venous symptoms. Symptoms can include pain, itching, swelling, paresthesia, a sensation of heaviness, and in severe cases, leg ulcers. After proximal DVT, an estimated 20–50% of people develop the syndrome, with 5–10% experiencing severe symptoms. Post-thrombotic syndrome can also be a complication of distal DVT, though to a lesser extent than with proximal DVT.
In the 10 years following an initial VTE, about 30% of people will have a recurrence. VTE recurrence in those with prior DVT is more likely to recur as DVT than PE. Cancer and unprovoked DVT are strong risk factors for recurrence. After initial proximal unprovoked DVT with and without PE, 16–17% of people will have recurrent VTE in the 2 years after they complete their course of anticoagulants. VTE recurrence is less common in distal DVT than proximal DVT. In upper extremity DVT, annual VTE recurrence is about 2–4%. After surgery, a provoked proximal DVT or PE has an annual recurrence rate of only 0.7%.
Epidemiology
About 1.5 out of 1000 adults a year have a first VTE in high-income countries. The condition becomes much more common with age. VTE rarely occurs in children, but when it does, it predominantly affects hospitalized children. Children in North America and the Netherlands have VTE rates that range from 0.07 to 0.49 out of 10,000 children annually. Meanwhile, almost 1% of those aged 85 and above experience VTE each year. About 60% of all VTEs occur in those 70 years of age or older. Incidence is about 18% higher in males than in females, though there are ages when VTE is more prevalent in women. VTE occurs in association with hospitalization or nursing home residence about 60% of the time, active cancer about 20% of the time, and a central venous catheter or transvenous pacemaker about 9% of the time.
During pregnancy and after childbirth, acute VTE occurs in about 1.2 of 1000 deliveries. Despite it being relatively rare, it is a leading cause of maternal morbidity and mortality. After surgery with preventive treatment, VTE develops in about 10 of 1000 people after total or partial knee replacement, and in about 5 of 1000 after total or partial hip replacement. About 400,000 Americans develop an initial VTE each year, with 100,000 deaths or more attributable to PE. Asian, Asian-American, Native American, and Hispanic individuals have a lower VTE risk than white or Black people. Populations in Asia have VTE rates at 15 to 20% of what is seen in Western countries, with an increase in incidence seen over time. In North American and European populations, around 4–8% of people have a thrombophilia, most commonly factor V Leiden and prothrombin G20210A. In China, Japan, and Thailand, deficiencies in protein S, protein C, and antithrombin predominate. Non-O blood type is present in around 50% of the general population and varies with ethnicity, and it is present in about 70% of those with VTE.
DVT occurs in the upper extremities in about 4–10% of cases, with an incidence of 0.4–1.0 cases per 10,000 a year. A minority of upper extremity DVTs are due to Paget–Schroetter syndrome, also called effort thrombosis, which occurs in 1–2 people out of 100,000 a year, usually in athletic males around 30 years of age or in those who do significant amounts of overhead manual labor.
Source: Wikipedia, The Free Encyclopedia · CC BY-SA 4.0
References
- Deep Vein Thrombosis — MedlinePlus, U.S. National Library of MedicineSource: MedlinePlus, National Library of Medicine Public domain (U.S. government work). Retrieved 2026-10-19.
- Deep vein thrombosis — Wikipedia, The Free EncyclopediaText from the Wikipedia article "Deep vein thrombosis" (CC BY-SA 4.0); excerpted. Licence. Retrieved 2026-10-19. Revision used.
Text above is quoted from the listed sources without changes to its meaning. Image credits and licences are shown with each image. Educational information only, not medical advice.
Related conditions
Educational overview, not medical advice. Treatment varies by person and location. Consult a qualified health professional for diagnosis or care. Content and model notes · Privacy information